Convalescent plasma futile as treatment for critically ill COVID-19 patients, study finds

In the earliest days of the COVID-19 pandemic, the medical community turned to a century-old treatment: Take blood from recovered patients and give it to the sick. The hypothesis was that components in the so-called “convalescent plasma” that fought off the disease once could do it again, something that has worked in other diseases, such as Ebola.
Today, an international research team, which included University of Pittsburgh School of Medicine physician-scientists and UPMC patients, effectively put an end to that practice with a clinical trial that concluded convalescent plasma is “futile” as a COVID-19 treatment for most critically ill patients. The results are published in JAMA concurrent with presentation at the European Society of Intensive Care Medicine’s annual meeting.
“There were biologically plausible reasons to turn to convalescent plasma early in the pandemic when hundreds of thousands of people were getting sick and treatments had yet to be discovered,” said co-lead author Bryan McVerry, M.D., associate professor of pulmonary, allergy and critical care medicine at Pitt and a UPMC intensivist. “Unfortunately, it was either being administered outside of clinical trials or in trials that weren’t focused on critically ill patients, slowing our ability to see if it actually worked. Finally, with these results, we can put an end to using convalescent plasma for our sickest COVID-19 patients and focus on treatments that we know work, as well as developing and testing better ones.”
The findings are the latest from REMAP-CAP (Randomised, Embedded, Multifactorial, Adaptive Platform Trial for Community-Acquired Pneumonia), which has enrolled thousands of patients in hundreds of hospitals around the world to quickly determine what COVID-19 treatments work best in which patients. To date, more than 400 UPMC patients have been enrolled. Among its discoveries, REMAP-CAP has shown that inexpensive steroids are effective in helping critically ill patients, while blood thinners help the moderately ill.
In the convalescent plasma trial, REMAP-CAP enrolled 2,011 adults hospitalized with severe COVID-19. They were randomized to either receive two units of convalescent plasma or no plasma and followed to see if the likelihood of surviving at least three weeks without needing organ support, such as a ventilator, differed based on whether they were treated or not.
The trial concluded for futility when enough data was collected to say with greater than 99% certainty that convalescent plasma did not help critically ill COVID-19 patients.
However, the results followed a slightly different pattern for the 126 patients who were immunocompromised. This group appeared to do slightly better with the convalescent plasma treatment compared to the standard treatment, but the number of patients was too small to make a definitive statement.
“It could be that patients with an impaired immune system, who are unable to mount an effective immune response, could still benefit from the antibodies present in blood plasma from COVID-recovered patients, especially early on in the illness,” said corresponding author Lise Estcourt, M.D., a associate professor of haematology and transfusion medicine at the Oxford University’s Radcliffe Department of Medicine and director of the U.K.’s National Health Service Blood and Transplant Clinical Trials Unit. “This is something that definitely warrants investigation.”
The researchers could not determine why convalescent plasma did not improve outcomes in most critically ill patients.
“We speculate that it could be a combination of too few high-quality antibodies in the plasma and these patients being too far along in their illness with a run-away inflammatory immune response for those antibodies to turn the tide,” said co-senior author Derek Angus, M.D., M.P.H., chief innovation officer at UPMC and chair of the Department of Critical Care Medicine at Pitt. “It is still possible that convalescent plasma helps people in earlier stages of illness, though it is likely not efficient to use given that monoclonal antibodies — which UPMC also is evaluating in our OPTIMISE-C19 adaptive trial — are such an effective treatment for early COVID-19.”
Additional co-authors of this research from Pitt or UPMC are David T. Huang, M.D., M.P.H., Kelsey Linstrum, M.S., Stephanie Montgomery, M.Sc., Christopher Seymour, M.D., M.Sc., John McDyer, M.D., and Darrell Triulzi, M.D. Authors at other institutions are listed in the JAMA manuscript.
This research was supported by the UPMC Learning While Doing Program, as well as multiple other funders listed in the JAMA manuscript.

Read more →

Calculating the path of cancer

Biologists at Cold Spring Harbor Laboratory (CSHL) are using a mathematical approach developed in CSHL Assistant Professor David McCandlish’s lab to find solutions to a diverse set of biological problems. Originally created as a way to understand interactions between different mutations in proteins, the tool is now being used by McCandlish and his collaborators to learn about the complexities of gene expression and the chromosomal mutations associated with cancer. McCandlish says:
“This is one of the things that’s really fascinating about mathematical research, is sometimes you can see connections between topics, which on the surface they seem so different, but at a mathematical level, they might be using some of the same technical ideas.”
All of these questions involve mapping the likelihood of different variations on a biological theme: which combinations of mutations are most likely to arise in a particular protein, for example, or which chromosome mutations are most often found together in the same cancer cell. McCandlish explains that these are problems of density estimation — a statistical tool that predicts how often an event happens. Density estimation can be relatively straightforward, such as charting different heights within a group of people. But when dealing with complex biological sequences, such as the hundreds, or thousands of amino acids that are strung together to build a protein, predicting the probability of each potential sequence becomes astonishingly complex.
McCandlish explains the fundamental problem his team is using math to address: “Sometimes if you make, say one mutation to a protein sequence, it doesn’t do anything. The protein works fine. And if you make a second mutation, it still works fine, but then if you put the two of them together, now you’ve got a broken protein. We’ve been trying to come up with methods to model not just interactions between pairs of mutations, but between three or four or any number of mutations.”
The methods they have developed can be used to interpret data from experiments that measure how hundreds of thousands of different combinations of mutations impact the function of a protein.
This study, reported in the Proceedings of the National Academy of Sciences, began with conversations with two other CSHL colleagues: CSHL Fellow Jason Sheltzer and Associate Professor Justin Kinney. They worked with McCandlish to apply his methods to gene expression and the evolution of cancer mutations. Software released by McCandlish’s team will enable other researchers to use these same approaches in their own work. He says he hopes it will be applied to a variety of biological problems.
Story Source:
Materials provided by Cold Spring Harbor Laboratory. Original written by Jennifer Michalowski. Note: Content may be edited for style and length.

Read more →

Pfizer Booster Can Be Given After 6 Months, European Drug Agency Says

The European Medicines Agency, the European Union’s main drug regulator, said on Monday that a booster shot of the Pfizer-BioNTech coronavirus vaccine can be given to healthy adults at least six months after the second dose.The agency said that data showed antibody levels increased in adults aged 18 to 55 with normal immune systems who received a third dose of the vaccine. It is still assessing booster shots of the Moderna vaccine.The agency also said that those with “severely weakened” immune systems can receive an extra dose of the Pfizer-BioNTech or Moderna vaccines as early as 28 days after the second dose. It is expected that an additional shot “would increase protection in at least some of the patients,” the agency said. The recommendation is based on studies showing that an extra dose of those vaccines could increase the ability to produce antibodies in organ transplant recipients.In the European Union, vaccination campaigns are a prerogative of national governments, and each of the 27 member nations can decide for themselves whether to give booster shots to all their adult residents. Some E.U. nations, such as France, Germany and Belgium, started giving extra doses to older people and those with weakened immune systems last month, while the Czech Republic and Hungary opened this possibility to all adults.Although the European Union has one of the highest vaccination rates in the world, with over 73 percent of adults fully inoculated, there is no coronavirus vaccine authorized yet for children. The European Center for Disease Prevention and Control warned last week that the average level of vaccination across the bloc is not sufficient to halt the virus from spreading if governments relax Covid-19 restrictions.The agency said it was carefully monitoring “very rare” side effects of a booster shot, such as inflammatory heart conditions, but that for the moment the risk is not yet known.The decisions of wealthier nations to administer booster shots while the rest of the world remains largely unvaccinated have raised alarm among health experts. Dr. Tedros Adhanom Ghebreyesus, the director general of the World Health Organization, has called for a moratorium on coronavirus vaccine booster shots for people who are not immunocompromised until at least the end of the year.

Read more →

Covid: Novavax jab volunteer's 'regret' over trial approval wait

SharecloseShare pageCopy linkAbout sharingImage source, ReutersA Covid vaccine trial volunteer has said he has been left struggling to organise trips abroad because the jab involved has not yet been licensed.Damian Reynolds, from Bradford, said he now “regretted” getting two doses of the Novavax jab in 2020 as he could not prove he had been fully vaccinated.The vaccine has yet to be licensed in the UK and some countries refuse to consider volunteers fully vaccinated.Novavax said it was “working day and night” to complete its submission.The US-based firm added it would “advocate” on behalf of UK volunteers who had taken part in its Covid vaccine trial.The company started its trials in October 2020, with over 15,000 people across the country taking part.But with the Novavax trial still ongoing and the vaccine not yet licensed in the UK, participants are classed by other countries in the same way as those who are unvaccinated.That means they may have to quarantine or complete tests before travelling abroad.Mr Reynolds said: “If I had not stepped aside to help out, I’d have had an approved vaccine by now and have the same freedoms as everyone else.”‘Second class citizen’Meanwhile, Liam Calland, another Novavax Covid vaccine trial participant, who is also from Yorkshire, said he felt “trapped”.Mr Calland said he had already had to defer a family holiday and now thought he would have to cancel it because of the uncertainty.”I feel a second class citizen with the way things are.”[It is] quite sad to tell your 10-year-old daughter we won’t be able to go because of something good I’ve done.”At the time the Novavax trials got under way, no Covid vaccines had been given approval by Britain’s medicines regulator, the Medicines and Healthcare products Regulatory Agency (MHRA). Vaccines developed by Pfizer/BioNTech, Janssen, Moderna and AstraZeneca have since been approved.In January, Novavax posted positive results for its UK trial, but it has not yet filed for approval and the trial remains ongoing.The company said it was still completing its concluding filings, which it hoped would be submitted in the next “couple of months”.The MHRA will then decide whether to approve the vaccine for use outside of trials.Novavax said it and the UK government felt people who took part in trials should be treated the same internationally as those who have had other, approved, vaccines.”Novavax is doing all we can to advocate on their behalf to support proof of vaccination outside of the UK,” it added.Follow BBC Yorkshire on Facebook, Twitter and Instagram. Send your story ideas to yorkslincs.news@bbc.co.uk.

Read more →

Specific UV light wavelength could offer low-cost, safe way to curb COVID-19 spread

A specific wavelength of ultraviolet (UV) light is not only extremely effective at killing the virus which causes COVID-19, but is also safer for use in public spaces, finds new University of Colorado Boulder research.
The study, published this month in Applied and Environmental Microbiology, is the first to comprehensively analyze the effects of different wavelengths of UV light on SARS-CoV-2 and other respiratory viruses, including the only wavelength safer for living beings to be exposed to without protection.
The findings, which the authors refer to as a “game changer” for UV light use, could lead to new affordable, safe and highly effective systems for reducing viral spread in crowded public spaces like airports and concert venues.
“Of almost every pathogen we have ever studied, this virus is one of the easiest, by far, to kill with UV light,” said senior author Karl Linden, professor of environmental engineering. “It takes a very low dose. This indicates that UV technology could be a really good solution for protecting public spaces.”
UV light is naturally emitted by the sun, and most forms are harmful to living beings — as well as microorganisms, like viruses. This light can get absorbed by the genome of an organism, tie knots in it and prevent it from reproducing. These harmful wavelengths from the sun, however, are filtered out by the ozone layer before they reach the surface of the Earth.
Some common products, like fluorescent tube lamps, use human-engineered UV light, but a white phosphorous coating on the inside protects people from the UV rays.

Read more →

New mouse model unlocks drug testing of hormone-sensitive human breast cancer

Scientists at the Medical College of Wisconsin Cancer Center and an international team of collaborators have generated mice with an improved hormone profile that supports growth and metastatic spread of implanted human breast tumors.
The majority of breast cancer deaths are caused by estrogen receptor(ER)-positive tumors. It has been a long-standing challenge to grow untreated ER-positive breast tumors from patients in mice. The shortage of such human breast tumor models has hampered efforts to identify better drugs or drug combinations. More effective treatments are needed to prevent the frequent development of resistance to current therapies and thereby reduce mortality from breast cancer.
ER-positive breast tumors are sensitive to the hormone prolactin, most known for promoting milk-production in mothers. The investigators had previously discovered that mouse prolactin fails to activate human prolactin receptors and speculated that this hormonal shortcoming was key to the poor growth of human ER-positive breast cancer in mice.
This new study reports that by modifying the mouse prolactin gene, the team generated a mouse breed that produces blood levels of human prolactin similar to the levels detected in patients. This new mouse model, called NSG-Pro, supports greatly enhanced growth of implanted ER-positive human breast cancers. Molecular pathway analyses of the tumors revealed that prolactin collaborates with estrogen and Her2, two well-established growth factors for breast cancer.
The team has now generated a panel of transplantable estrogen-dependent patient-derived breast tumor models in NSG-Pro mice. Several of the new tumor lines recapitulate disease progression in patients by spreading to distant organs when implanted into the mammary glands of NSG-Pro mice. The research appears in the September 15 online issue of the journal Science Advances.
“We are particularly excited about the opportunity to study distant metastases and test the effectiveness of drugs on advanced stage ER-positive breast cancer, because until now such experimental models have not been available,” says Hallgeir Rui, WBCS Endowed Professor of Breast Cancer Research; director of the MCW Tissue Bank; and professor and vice chair of Research, Pathology at MCW. “This is particularly important because breast cancer patients die from distant metastases.”
Intriguingly, after surgically removing the primary tumors from the mouse mammary glands, the team documented that two different prolactin-blocking treatments inhibited the growth of cancer cells that had spread to the lungs. While further studies are needed, the results raise the prospect that prolactin-targeted drugs may benefit some patients with metastatic ER-positive breast cancer.
“The NSG-Pro mouse model provides previously inaccessible precision medicine approaches for ER-positive human breast cancers,” said Yunguang Sun, MD, PhD, joint lead author of the study and assistant professor in Pathology & Laboratory Medicine at MCW.
Story Source:
Materials provided by Medical College of Wisconsin. Note: Content may be edited for style and length.

Read more →

Treating severe depression with on-demand brain stimulation

The study, which appears in the Oct. 4, 2021, issue of Nature Medicine, represents a landmark success in the years-long effort to apply advances in neuroscience to the treatment of psychiatric disorders.
“This study points the way to a new paradigm that is desperately needed in psychiatry,” said Andrew Krystal, PhD, professor of psychiatry and member of the UCSF Weill Institute for Neurosciences. “We’ve developed a precision-medicine approach that has successfully managed our patient’s treatment-resistant depression by identifying and modulating the circuit in her brain that’s uniquely associated with her symptoms.”
Previous clinical trials have shown limited success for treating depression with traditional deep brain stimulation (DBS), in part because most devices can only deliver constant electrical stimulation, usually only in one area of the brain. A major challenge for the field is that depression may involve different brain areas in different people.
What made this proof-of-principle trial successful was the discovery of a neural biomarker — a specific pattern of brain activity that indicates the onset of symptoms — and the team’s ability to customize a new DBS device to respond only when it recognizes that pattern. The device then stimulates a different area of the brain circuit, creating on-demand, immediate therapy that is unique to both the patient’s brain and the neural circuit causing her illness.
This customized approach alleviated the patient’s depression symptoms almost immediately, Krystal said, in contrast to the four- to eight-week delay of standard treatment models and has lasted over the 15 months she has had the implanted device. For patients with long-term, treatment-resistant depression, that result could be transformative.
“I was at the end of the line,” said the patient, who asked to be known by her first name, Sarah. “I was severely depressed. I could not see myself continuing if this was all I’d be able to do, if I could never move beyond this. It was not a life worth living.”
Applying Proven Advances in Neuroscience to Mental Health

Read more →

When the western US burns, the east also gets sick

While most of the largest U.S. wildfires occur in the Western U.S., almost three-quarters of the smoke-related deaths and visits to the emergency room for asthma occur east of the Rocky Mountains.
Smoke exposure, whether from wildfires or local burning, contributes to health problems across the U.S., but the impacts vary by region. A new study finds that smoke contributes to a larger percentage of health problems in the West, but affects greater numbers of people in the East — possibly when they aren’t even aware of the smoky air.
The new study was published in GeoHealth, AGU’s journal investigating the intersection of human and planetary health for a sustainable future.
In the West, where population density is generally lower and smoke concentrations are typically higher, smoke played a larger role in the number of asthma complaints and ER visits, contributing to more than 1% of annual visits in some years. In the East, with its high population density and lower smoke concentrations, there were a higher number of visits overall, even though a smaller percentage were related to smoke (0.3% to 0.6%).
The researchers estimate that long-term smoke exposure results in about 6,300 extra deaths each year, with the highest numbers occurring in the most populous states. Only 1,700 of those deaths occurred in the West.
Fires throw tremendous amounts of pollutants into the air, including toxic gases and soot. Smoke contains tiny particles smaller than 2.5 microns, called PM2.5, that enter the lungs and contribute to multiple health problems. Short-term exposure to PM2.5 from smoke is linked to respiratory health problems, like asthma attacks, and the long-term effects of PM2.5 from smoke are not fully understood. Research on PM2.5 from urban pollution suggests that exposure is linked to lung cancer, heart disease and an overall higher chance of death.

Read more →

Brain implant may lift most severe depression

SharecloseShare pageCopy linkAbout sharingImage source, Maurice Ramirez, UCSF 2021An electrical implant that sits in the skull and is wired to the brain can detect and treat severe depression, US scientists believe after promising results with a first patient. Sarah, who is 36, had the device fitted more than a year ago and says it has turned her life around. The matchbox-sized pack in her head is always “on” but only delivers an impulse when it senses she may need it. The experimental study is described in Nature Medicine journal. The researchers, from University of California, San Francisco, stress it is too soon to say if it might help other patients, like Sarah, with hard-to-treat depression, but they are hopeful and plan more trials. Depression circuitsSarah is the first person to have had the experimental therapy. She’d had a succession of failed treatments, including anti-depressants and electroconvulsive therapy in recent years. The surgery may sound daunting, but Sarah said the prospect of gaining “any kind of relief” was better than the darkness she had been experiencing.Image source, John Lok, UCSF 2021″I had exhausted all possible treatment options. “My daily life had become so restricted. I felt tortured each day. I barely moved or did anything.”The surgery involved drilling small holes in her skull to fit the wires that would monitor and stimulate her brain. The box, containing the battery and the pulse generator, was tucked into the bone, beneath her scalp and hair.The procedure took a full working day and was done under general anaesthetic, meaning Sarah was unconscious throughout. Sarah says when she woke, up she felt euphoric. “When the implant was first turned on, my life took an immediate upward turn. My life was pleasant again. “Within a few weeks, the suicidal thoughts disappeared. “When I was in the depths of depression all I saw is what was ugly.”A year on, Sarah remains well, with no side-effects.”The device has kept my depression at bay, allowing me to return to my best self and rebuild a life worth living.”She can’t feel the device as it fires, but says: “I could probably tell you within 15 minutes that it has gone off because of a sense of alertness and energy or the positivity I will feel.”How it worksResearcher Dr Katherine Scangos, who is a psychiatrist at the university, said the innovation was made possible by locating the “depression circuits” in Sarah’s brain. “We found one location, which is an area called the ventral striatum, where stimulation consistently eliminated her feelings of depression. “And we also found a brain activity area in the amygdala that could predict when her symptoms were most severe.”The scientists say a lot more research is needed to test the experimental therapy and determine if it can help more people with severe depression, and perhaps other conditions too. Personalised treatmentDr Scangos, who has enrolled two other patients in the trial and hopes to recruit nine more, said: “We need to look at how these circuits vary across patients and repeat this work multiple times. “And we need to see whether an individual’s biomarker or brain circuit changes over time as the treatment continues.”We didn’t know if we were going to be able to treat her depression at all because it was so severe. “So in that sense we are really excited about this. It’s so needed in the field right now.”Dr Edward Chang, the neurosurgeon who fitted the device, said: “To be clear, this is not a demonstration of efficacy of this approach. “It’s really just the first demonstration of this working in someone and we have a lot of work ahead of us as a field to validate these results to see if this actually is something that will be enduring as a treatment option.”Prof Jonathan Roiser, a neuroscience expert at University College London in the UK, said: “Although this kind of highly invasive surgical procedure would only ever be used in the most severe patients with intractable symptoms, it is an exciting step forward due to the bespoke nature of the stimulation. “It is likely that if trialled in other patients, different recording and stimulation sites would be required, as the precise brain circuitry underlying symptoms probably varies between individuals. “As there was only one patient and no control condition, it remains to be seen whether these promising results hold in clinical trials.”Related Internet LinksGet help from a mental health charity – NHSNature MedicineThe BBC is not responsible for the content of external sites.

Read more →

A ‘Pacemaker for the Brain’: No Treatment Helped Her Depression — Until This

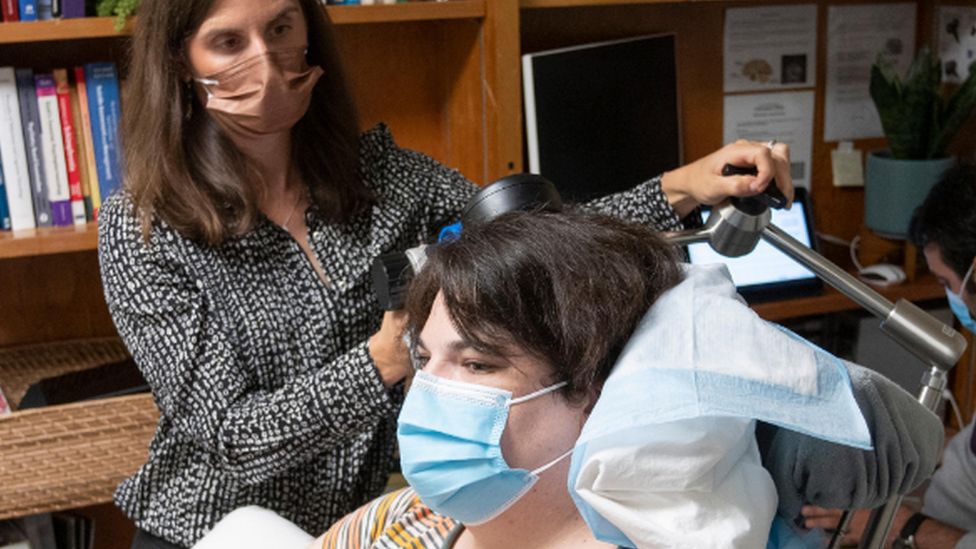
It’s the first study of individualized brain stimulation to treat severe depression. Sarah’s case raises the possibility the method may help people who don’t respond to other therapies.Driving home from work in Northern California five years ago, a young woman was so overwhelmed with depression that all she could think about was ending her life.“I couldn’t stop crying,” recalled Sarah, now 38. “The thought that consumed me the entire way on that road was just driving my car into the marshland so I can drown.”She made it home, but soon after, moved in with her parents because doctors considered it unsafe for her to live alone. No longer able to function at work, she quit her health technology job.She tried nearly every treatment: roughly 20 different medications, months in a hospital day program, electroconvulsive therapy, transcranial magnetic stimulation. But as with nearly a third of the more than 250 million people with depression worldwide, her symptoms persisted. Then Sarah became the first participant in an unusual study of an experimental therapy. Now, her depression is so manageable that she’s taking data analysis classes, has moved to her own place and helps care for her mother, who suffered a fall.“Within a few weeks, the suicidal thoughts just disappeared,” said Sarah, who asked to be identified by only her first name to protect her privacy. “Then it was just a gradual process where it was like my lens on the world changed.”Researchers at the University of California, San Francisco surgically implanted a battery-operated, matchbook-sized device in Sarah’s brain — a “pacemaker for the brain” some call it — calibrated to detect the neural activity pattern that occurs when she is becoming depressed. It then delivers pulses of electrical stimulation to stave off depression.Twelve days after Sarah’s device was fully operational in August 2020, her score on a standard depression scale dropped to 14 from 33, and several months later, it fell below 10, essentially signaling remission, the researchers reported.“The device has kept my depression at bay, allowing me to return to my best self and rebuild a life worth living,” Sarah said.Sarah’s is the first documented case of personalizing a technique called deep brain stimulation to successfully treat depression. Much more research is needed before it’s clear how effective the approach could be and for how many patients. But several teams of scientists are now working on ways to essentially match the electrical stimulation to what happens in an individual patient’s brain.Deep brain stimulation is used to treat Parkinson’s disease and several other disorders, but isn’t approved by federal regulators for depression because results have been inconsistent. While some previous studies suggested benefits, two trials sponsored by U.S. device companies were stopped in the last decade because stimulation seemed no better than the placebo effect of a “sham” implant that provided no stimulation.But those studies didn’t target individualized locations or patterns of electrical activity in people’s brains. It was “one size fits all,” said Dr. Darin Dougherty, director of neurotherapeutics at Massachusetts General Hospital, who worked on one of the halted trials. He called the personalized approach with Sarah, which he wasn’t involved in, “very exciting.”“One person’s depression might look very different from another person’s depression,” said Dr. Katherine Scangos, an assistant professor of psychiatry at U.C.S.F. and an author of a report about Sarah’s case, published Monday in the journal Nature Medicine. The senior authors were Dr. Andrew Krystal, an expert in neuro-modulation and mood disorders, and Dr. Edward Chang, whose work includes brain implants for paralyzed patients who cannot speak.To identify the specific brain activity pattern linked to Sarah’s depression, researchers conducted an intensive 10-day exploration of Sarah’s brain, placing multiple electrodes in it and asking about her feelings when they applied stimulation to different locations in varying doses.“One person’s depression might look very different from another person’s depression,” said Dr. Katherine Scangos, a researcher on a new study using deep brain stimulation as a personalized treatment.Mike Kai Chen for The New York TimesSarah remembers an “aha moment” when she felt like “the Pillsbury Doughboy,” emitting a “giant belly laugh,” which she said was “the first time I spontaneously laughed and smiled” in five years. Another feeling resembled “being in front of warm fire and reading a comforting book,” while a negative sensation felt like “nails on a chalkboard.”Eventually, the team identified a specific pattern of electrical activity that coincided with Sarah becoming depressed.The exploratory phase guided the researchers to place the stimulation device in Sarah’s right brain hemisphere linked to electrodes in two regions. One was the the ventral striatum, involved in emotion, motivation and reward, where stimulation “consistently eliminated her feelings of depression,” and the other the amygdala, where changes could “predict when her symptoms were most severe,” Dr. Scangos said.While deep brain stimulation is typically delivered continuously, Sarah’s device is set to supply only a six-second burst when it recognizes her depression-linked brain activity pattern. The goal, said Dr. Dougherty, is that stimulation will disrupt or shift the neural activity to produce a healthier pattern that will ease depressive symptoms.Sarah has continued taking psychiatric medications, and the stimulation hasn’t eliminated depression-causing activity in her brain. But she can manage her illness much better, she said, instead of being unable to make even the smallest decisions, like what to eat.Now, “you’re experiencing that whole negative, depressive, whatever the triggering thing is, and then it’s like suddenly the ultra-rational side of you comes on and those emotions can be separated,” she said in an interview, wearing a T-shirt that said “Take it easy lemon squeezy.”That separation helps her productively use tools from talk therapy, like staying calm and maintaining perspective.About 30 percent of people with depression don’t respond to standard treatments or find the side effects intolerable. Deep brain stimulation wouldn’t be appropriate for all because it costs tens of thousands of dollars and brain surgery to implant the device carries risks like infection. But if the new attempts work, it might help a significant number, experts said. Dr. Chang said the research may also lead to noninvasive approaches that would help more people.“Our job now is really to figure out what is it that identifies who needs this kind of intervention,” said Dr. Helen Mayberg, director of the Center for Advanced Circuit Therapeutics at the Icahn School of Medicine in New York City, who pioneered the concept of deep brain stimulation for depression nearly 20 years ago.Dr. Mayberg uses a different method of individualization. With imaging, she finds the location in each person’s brain where four white matter bundles intersect near a key depression-related region. After implanting electrodes and a stimulation device, “we pretty much set it and forget it,” delivering stimulation continuously, while also helping patients with conventional therapy.Dr. Scangos examined a graph of Sarah’s brain activity. Mike Kai Chen for The New York TimesNeural activity is monitored “to learn the brain signature that heralds an impending depressive relapse or need for a dose adjustment or just indicates that the person is just having a bad week,” Dr. Mayberg said. She led one of the halted trials, but her work has also allowed patients to experience improvements that continue for years if stimulation is sustained.In another approach, Dr. Sameer Sheth, an associate professor of neurosurgery at Baylor College of Medicine, and colleagues study a patient’s specific brain activity pattern to identify which of billions of combinations of stimulation characteristics, like frequency and amplitude, improve that patient’s depression.He then tunes electrodes in two regions and applies that specific combination as continuous stimulation.Dr. Sheth said the first patient, given the device in March 2020, “is remarkably well” now, maintaining a relationship and becoming a father. To test for a placebo effect, researchers gradually stopped stimulation to one brain region without the patient knowing when. His depression “got worse and worse” said Dr. Sheth, until he needed “rescue.” After stimulation restarted, he improved, suggesting the effect “is definitely stimulation-related.”Several months ago, Sarah needed a rescue too. Shortly after entering a study phase where the device is either turned off or left on for six weeks without the participant knowing which, “the suicidal thoughts were back,” Sarah said. Her family tried to get her hospitalized, but hospitals were full. “Things were really bad,” Sarah said.“She did have a very severe worsening of her depression,” said Dr. Scangos. She said she couldn’t disclose whether stimulation had been off or on, but said a device company technician was sent to Sarah’s home to “make a rescue change.”Afterward, Sarah said, she improved again.Over the year, the number of times a day that Sarah’s device has detected depression-linked brain activity and delivered stimulation has decreased somewhat, but is still substantial, Dr. Scangos said. Still, some days Sarah doesn’t need the maximum amount the device is set to provide: 300 times or 30 total minutes daily. (It automatically stops around 6 p.m. because evening stimulation made her too alert to sleep.)Longer-term and more detailed data on Sarah will be published later, said the researchers, who have two other participants so far. The device is intentionally tuned so Sarah cannot feel the stimulation, but she believes she knows that it’s occurred because she subsequently develops a sense of “emotional distance” that keeps negative feelings “compartmentalized,” she said.Also, “I feel alert,” she said. “I feel present.” That’s “a really good sign,” said Dr. Dougherty, who is considering using a similar approach for depression and possibly addiction. “The emotions are still there, but instead of sticking like mud, it’s running off like water.”To help researchers correlate brain activity with emotional states, two or three times a day, Sarah holds a doughnut-shaped magnet to her head, triggering the device to save the next 90 seconds of neural activity, and she completes a mental health survey. She’s been encouraged to pick moments “when she’s in a very good mood or a bad mood,” Dr. Scangos said. Also, twice daily, 12 minutes of neural data are automatically relayed to the device company and researchers.One question, experts said, is whether Sarah’s results support the theory that stimulating briefly whenever depression begins works because it keeps the brain from becoming accustomed to the treatment. Or, Dr. Sheth asked, does Sarah’s need for many daily doses after a year suggest continuous stimulation would be as or more effective?Another question is whether the therapy can prompt lasting brain changes to eventually avert depression with little or no continuing stimulation.Because of her implanted device that delivers deep brain stimulation, Sarah has been able to move to her own apartment and take classes in data analysis.Ruth Fremson/The New York TimesResearchers, several of whom consult for device companies or have patents related to deep brain stimulation, expect it will take years to learn if individualized approaches are effective enough to be approved. Different methods might work for different people’s depression, and individualized stimulation might eventually help other psychiatric disorders, researcher say. The most elemental things have improved for Sarah, who said she’s started to “relearn my life” and that “hobbies I used to distract myself from suicidal thoughts suddenly became pleasurable again.” When depressed, Sarah, a passionate cook and foodie, had such slow reflexes and trouble functioning that she’d cut or burn herself in the kitchen and doctors told her it wasn’t safe to cook anymore. Foods had little flavor. But after receiving the device, she ate Vietnamese pho in the hospital cafeteria and was thrilled she could taste “the brightness and the herbs,” she said. While being driven home from the hospital, she saw the marshes and exclaimed: “God, the color differentiation is gorgeous.” Now, she said, she’s “seeing things that are beautiful in the world, and when I was in the depths of depression, all I saw was what was ugly.”If you are having thoughts of suicide, call the National Suicide Prevention Lifeline at 1-800-273-8255 (TALK) or go to SpeakingOfSuicide.com/resources for a list of additional resources.

Read more →