A study of skull growth and tooth emergence reveals that timing is everything

Six, 12, and 18. These are the ages that most people get their three adult molars or large chewing teeth towards the back of the mouth. These teeth come in at a much later age than they do in our closest living relative, the chimpanzee, who get those same adult molars at around three, six, and 12 years old. Paleoanthropologists have wondered for a long time how and why humans evolved molars that emerge into the mouth at these specific ages and why those ages are so delayed compared to living apes. Scientists at the University of Arizona and Arizona State University unveil a study in Science Advances this week that they think has finally cracked the case.
Humans are unusual primates. We are highly intelligent, extremely social, remarkably resourceful, able learners, skilled teachers, and as a result, a remarkable evolutionary success story. A key aspect of our biology allowing these components of the human experience to evolve is our unique “life history,” or the overall pace of life, including how fast we grow, how long we are dependent on mothers for nutritional support, how long it takes us to reach sexual maturity, and how long we live. Amazingly, clues to most of these components of our human biology are connected with our teeth.
The one dental feature intimately associated with the pace of growth and life history is the ages at which our adult molars cut through the gumline. For many decades, evolutionary anthropologists have leveraged the very tight relationship — which exists across all primates — between the pace at which these adult molars emerge into the mouth with the overall pace of life. Modern humans, for instance, grow up incredibly slowly, have a very long and protracted life history, and emerge their adult molars very late in life, later than any other living or extinct primate.
“One of the mysteries of human biological development is how the precise synchrony between molar emergence and life history came about and how it is regulated,” said Halszka Glowacka, lead author and assistant professor at the University of Arizona, College of Medicine-Phoenix.
Glowacka and paleoanthropologist Gary Schwartz, a researcher with the Institute of Human Origins and professor in the School of Human Evolution and Social Change, published their study this week that provides the first clear answer — it is the coordination between facial growth and the mechanics of the chewing muscles that determines not just where but when adult molars emerge. This delicate dance results in molars coming in only when enough of a “mechanically safe” space is created. Molars that emerge “ahead of schedule” would do so in a space that, when chewed on, would disrupt the fine-tuned function of the entire chewing apparatus by causing damage to the jaw joint.
For the study, Glowacka and Schwartz created 3D biomechanical models of skulls, including the attachment positions of each major chewing muscle, throughout the growth period in nearly two dozen different species of primates ranging from small lemurs to gorillas. When combined with details about the rates of jaw growth in these species, their integrative models revealed the precise spatial relationship and temporal synchrony of each emerging molar within the context of the growing and shifting masticatory system.
The authors note that this research establishes two things — it convincingly demonstrates that it is the precise biomechanical relationship between growing faces and growing chewing muscles that results in the tight and predictive relationship between dental development and life history, and it reveals that our species’ delayed molar emergence schedules are a result of the evolution of overall slow growth coupled with short jaws and retracted faces — faces situated directly beneath our braincase.
Their study revealed that the combination of how fast jaws grow with how long or protruding jaws will ultimately become in adults determines the timing of when molars will emerge. Modern humans are special among primates given our prolonged growth profiles and our retracted faces with short dental arcades.
“It turns out that our jaws grow very slowly, likely due to our overall slow life histories and, in combination with our short faces, delays when a mechanically safe space — or a ‘sweet spot’ if you will — is available, resulting in our very late ages at molar emergence,” said Schwartz.
“This study provides a powerful new lens through which the long-known linkages among dental development, skull growth and maturational profiles can be viewed,” said Glowacka.
The researchers plan to apply their model to fossil human skulls to answer questions about when slowed jaw growth and delayed molar emergence first appeared in our fossil ancestors.
They also realize that the approach taken in this study could have implications for clinical dentistry. Because molars do not emerge until a point when enough facial growth has occurred and the sweet spot appears, “the finer details of the model could be explored in more samples to help understand the phenomenon of impacted wisdom teeth in humans,” noted Glowacka.

Read more →

Tiny bubbles can be future treatment for inflammation

Scientists hope that tiny sacs of material excreted by cells — so-called extracellular vesicles — can be used to deliver drugs inside the body. Researchers at Karolinska Institutet now show that these nano-bubbles can transport protein drugs that reduce inflammation caused by different diseases. The technique, which is presented in Nature Biomedical Engineering, shows promising results in animal models.
Extracellular vesicles (EVs) are important in inter-cellular communication as carriers of biological signals. They are nanometre-sized membrane-coated packages excreted by cells that can deliver fatty acids, proteins and genetic material to different tissues.
The tiny bubbles are found naturally in bodily fluids, are able to pass through biological barriers, like the blood-brain barrier, and can be used as natural carriers of therapeutic substances. Consequently, EVs have garnered growing interest as potential drugs.
MS and IBD
Using biomolecular techniques, researchers at Karolinska Institutet have coated the outer EV membrane with therapeutic proteins, more precisely receptors that bind to the inflammatory substances TNF-α and interleukin 6 (IL 6).
TNF-α and IL 6 form in the body under inflammatory conditions such as multiple sclerosis (MS) and inflammatory bowel disease (IBD), and play a key part in inflammation and the subsequent tissue damage. This knowledge has resulted in the development of biological drugs that dampen the inflammatory response by inhibiting TNF-α and IL 6.

Read more →

Protecting the ozone layer is delivering vast health benefits

An international agreement to protect the ozone layer is expected to prevent 443 million cases of skin cancer and 63 million cataract cases for people born in the United States through the end of this century, according to new research.
The research team, by scientists at the National Center for Atmospheric Research (NCAR), ICF Consulting, and U.S. Environmental Protection Agency (EPA), focused on the far-reaching impacts of a landmark 1987 treaty known as the Montreal Protocol and later amendments that substantially strengthened it. The agreement phased out the use of chemicals such as chlorofluorocarbons (CFCs) that destroy ozone in the stratosphere.
Stratospheric ozone shields the planet from harmful levels of the Sun’s ultraviolet (UV) radiation, protecting life on Earth.
To measure the long-term effects of the Montreal Protocol, the scientists developed a computer modeling approach that enabled them to look to both the past and the future by simulating the treaty’s impact on Americans born between 1890 and 2100. The modeling revealed the treaty’s effect on stratospheric ozone, the associated reductions in ultraviolet radiation, and the resulting health benefits.
In addition to the number of skin cancer and cataract cases that were avoided, the study also showed that the treaty, as most recently amended, will prevent approximately 2.3 million skin cancer deaths in the U.S.
“It’s very encouraging,” said NCAR scientist Julia Lee-Taylor, a co-author of the study. “It shows that, given the will, the nations of the world can come together to solve global environmental problems.”
The study, funded by the EPA, was published in ACS Earth and Space Chemistry. NCAR is sponsored by the National Science Foundation.

Read more →

Cancer costs US more than $156 billion annually, with drugs a leading expense

Care for the 15 most prevalent types of cancer in the U.S. cost approximately $156.2 billion in 2018, according to a team of Penn State College of Medicine researchers. The team also found that medication was the biggest expense and that medication expense for breast, lung, lymphoma and colorectal cancers incurred the most costs.
In a study, the researchers examined a database that included statistics on cancer care for the 402,115 privately insured cancer patients younger than 65 in the U.S. The aim of the study was to gather this data to help understand how money is being spent on cancer care. This information traditionally has been difficult to track, mainly because the U.S. has different ways to cover healthcare costs, such as private insurance for people less than 65 years of age and Medicare for people aged 65 and over, according to Dr. Nicholas Zaorsky, assistant professor from the Departments of Radiation Oncology and Public Health Sciences at the College of Medicine and researcher at Penn State Cancer Institute.
“The public often hears that the U.S. spends an inordinate amount of money on health care, but no one has quantified exactly how big that number is and how is that number broken down for exactly what types of services,” said Zaorsky, who is an associate of the Institute for Computational and Data Sciences. “Cancer is a leading cause of death, actually overtaking heart disease as the leading cause of death in the U.S. over the past few years. But, it’s still unknown what we pay for in cancer care. As a team, we wanted to look at what private insurances are paying for each kind of cancer and for each type of service. We also wanted to look at what are the greatest number of services performed and how much does each one of those services cost.”
The researchers, who report their findings today (Oct. 6) in JAMA Network Open, said that the database included 38.4 million types of procedures — or common procedural terminology (CPT) codes — for the 15 cancers, which include breast, prostrate, colorectal, lung, lymphoma, melanoma, uterus, head and neck, bladder, kidney, thyroid, stomach, liver, pancreas and esophagus cancers. The cohort study used 2018 data — the most recent complete numbers available — from the IBM Watson Health MarketScan. The sample included 27.1 million privately insured individuals, including patients diagnosed with the most prevalent cancers.
Breast cancer incurred the most services, about 10.9 million services and procedures, followed by colorectal cancer, which had approximately 3.9 million services listed in the database. Breast cancer was also the most expensive type of cancer, costing a total of $3.4 billion, followed by lung cancer and colorectal cancer, which were both estimated to incur around $1.1 billion in costs.
According to the researchers, drug costs represent the most expensive category for treating cancer patients. About $4 billion were spent on drugs to treat cancer, which is double the $2 billion paid out for surgeries.
The study was not meant to assess whether the spending on drugs — or any of the services — was cost-effective, although Zaorsky said the study may help guide future research into the subject.
“It’s hard to say like what is a reasonable price for a drug or service, but I think it’s fair to say that they make up the plurality of our health care spending in the U.S., then some would argue that this money may be better spent elsewhere in other services,” said Zaorsky. “These figures basically just show you how much the medical system spends on certain types of cancers versus another one. You might ask if these costs are justified. For example, pancreatic cancer is one of the deadliest cancers, but the total cost of care that we devote to pancreatic cancer is relatively low versus something like indolent prostate cancer.”
Story Source:
Materials provided by Penn State. Original written by Matt Swayne. Note: Content may be edited for style and length.

Read more →

Think a census of humans is hard? Try counting their brain cells!

In 2013, the U.S. government began investing $100 million to decipher how the human brain works in a collaborative project called the BRAIN Initiative. Cold Spring Harbor Laboratory (CSHL) and other researchers built tools and set standards for describing all the cells in the brain. On October 7, 2021 the initiative reached a major milestone, publishing a comprehensive census of cell types in the mouse, monkey, and human primary motor cortex in Nature.
The BRAIN Initiative Cell Census Network (BICCN) is the consortium of neuroscientists, computational scientists, physicists, geneticists, and instrument makers within the BRAIN Initiative tasked with counting and mapping all the cells in the brain.
Z. Josh Huang, an adjunct professor at CSHL, leads one branch of the BICCN that includes five principal investigators from CSHL and researchers from other institutions. His lab outlined ways to classify new cell subtypes within the mouse forebrain based on their shapes, connections, and the genes they use.
CSHL Professor Partha Mitra and other CSHL collaborators taught a computer to recognize different parts of neurons, then mapped the cells onto a topological world to see how those neurons are likely to connect.
CSHL Associate Professor Jesse Gillis’ lab developed a statistics-based computer tool to categorize cells based on similarities in their component parts. This program, called MetaNeighbor, uses RNA transcripts (the instructions to build the components) to compare and categorize mammalian brain cells.
CSHL Professor Anthony Zador’s lab developed MAPseq to map how different brain cells connect and interact. Several years later, Zador and his team developed BARseq and BARseq2, which can map connections and gene-use in thousands of neurons in a single mouse at single-neuron resolution.
CSHL Associate Professor Pavel Osten leads another branch of the BICCN dedicated to finding anatomical differences between female and male mouse brains. He and his lab developed qBrain, a method that combines brain imaging techniques to map cells and connections of the mouse primary motor cortex in three dimensions.
The atlases and catalogs published by the BICCN so far are frameworks upon which neuroscientists can now build. Neuroanatomists will be able to compare the human brain to the brains of other species. The BICCN scientists hope that within the next ten years, thousands of human brains will be mapped. This knowledge could be harnessed to study and treat schizophrenia, depression, Alzheimer’s, and traumatic brain injuries, and will be revolutionary to the future of neuroscience as a whole.
Story Source:
Materials provided by Cold Spring Harbor Laboratory. Original written by Jasmine Lee. Note: Content may be edited for style and length.

Read more →

Of two common weight loss surgeries, one is safer but less effective

When comparing two of the most common weight loss surgeries, a research team led by University of Michigan Health found that long-term, sleeve gastrectomy is safer than gastric bypass for Medicare patients.
Five years after each procedure, patients who’d undergone a sleeve gastrectomy, which involves removing part of the stomach, had a lower risk of death and complications than those who had chosen to have their stomachs divided into pouches through a gastric bypass surgery.
However, gastric bypass was superior in one area: Sleeve gastrectomy patients were more likely to need follow-up surgery, which could indicate that gastric bypass is more effective long-term, even though it carries more risks.
“It’s really important for patients to understand the risk of significant issues like death, complications, and hospitalization after these two procedures because that helps inform the decision about which type of bariatric surgery to choose,” said Ryan Howard, M.D., a general surgery resident at Michigan Medicine and the first author of the study.
“You could envision a scenario where a patient is averse to that risk, and so even if a sleeve gastrectomy doesn’t confer as much weight loss, they may want it because it’s the safer surgery,” Howard added. “On the other hand, if a patient has a lot of comorbidities, and a bypass is going to afford a better clinical benefit, maybe that risk is worth it.”
Short-term studies have shown that sleeve gastrectomy is the safer choice, but this study is one of the largest to analyze the outcomes of the two operations over a longer period of time.
Story Source:
Materials provided by Michigan Medicine – University of Michigan. Original written by Mary Clare Fischer. Note: Content may be edited for style and length.

Read more →

Historic go-ahead for malaria vaccine to protect African children

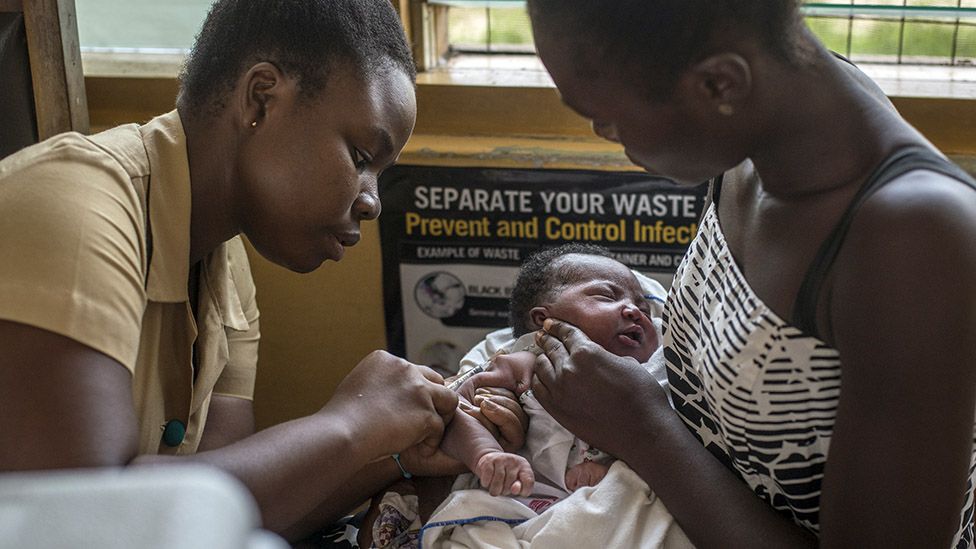
SharecloseShare pageCopy linkAbout sharingImage source, CRISTINA ALDEHUELAChildren across much of Africa are to be vaccinated against malaria in a historic moment in the fight against the deadly disease.Malaria has been one of the biggest scourges on humanity for millennia and mostly kills babies and infants. Having a vaccine – after more than a century of trying – is among medicine’s greatest achievements.The vaccine – called RTS,S – was proven effective six years ago.Now, after the success of pilot immunisation programmes in Ghana, Kenya and Malawi, the World Health Organization says the vaccine should be rolled out across sub-Saharan Africa and in other regions with moderate to high malaria transmission. Dr Tedros Adhanom Ghebreyesus, director-general of the WHO, said it was “a historic moment”. “The long-awaited malaria vaccine for children is a breakthrough for science, child health and malaria control,” he said. “[It] could save tens of thousands of young lives each year.”Deadly parasiteMalaria is a parasite that invades and destroys our blood cells in order to reproduce, and it’s spread by the bite of blood-sucking mosquitoes.Drugs to kill the parasite, bed-nets to prevent bites and insecticides to kill the mosquito have all helped reduce malaria.But the greatest burden of the disease is felt in Africa, where more than 260,000 children died from the disease in 2019. It takes years of being repeatedly infected to build up immunity and even this only reduces the chances of becoming severely ill.Dr Kwame Amponsa-Achiano piloted the vaccine in Ghana to assess whether mass vaccination was feasible and effective.”It is quite an exciting moment for us, with large scale vaccination I believe the malaria toll will be reduced to the barest minimum,” he said.Constantly catching malaria as a child inspired Dr Amponsa-Achiano to become a doctor in Ghana.”It was distressing, almost every week you were out of school, malaria has taken a toll on us for a long time,” he told me.Saving children’s livesThere are more than 100 types of malaria parasite. The RTS,S vaccine targets the one that is most deadly and most common in Africa: Plasmodium falciparum.Trials, reported in 2015, showed the vaccine could prevent around four in 10 cases of malaria, three in 10 severe cases and lead to the number of children needing blood transfusions falling by a third. However, there were doubts the vaccine would work in the real world as it requires four doses to be effective. The first three are given a month apart at five, six and seven months old, and a final booster is needed at around 18 months.Image source, BRIAN ONGOROThe findings of the pilots were discussed by two expert advisory groups at the WHO on Wednesday.The results, from more than 2.3 million doses, showed:the vaccine was safe and still led to a 30% reduction in severe malariait reached more than two-thirds of children who don’t have a bed-net to sleep underthere was no negative impact on other routine vaccines or other measures to prevent malariathe vaccine was cost-effective”From a scientific perspective, this is a massive breakthrough, from a public health perspective this is a historical feat,” said Dr Pedro Alonso, the director of the WHO Global Malaria Programme.”We’ve been looking for a malaria vaccine for over 100 years now, it will save lives and prevent disease in African children.”Why is malaria so hard to beat?Having just seen the world develop Covid vaccines in record time, you might be wondering why it has taken so long with malaria?Malaria is caused by a parasite which is far more insidious and sophisticated than the virus that causes Covid. Comparing them is like comparing a person and a cabbage.The malaria parasite has evolved to evade our immune system. That’s why you have to catch malaria time and time again before starting to get even limited protection. It has a complicated life cycle across two species (humans and mosquitoes), and even inside our body it morphs between different forms as it infects liver cells and red blood cells.Developing a malaria vaccine is like nailing jelly to a wall and RTS,S is only able to target the sporozoite form of the parasite (this is the stage between being bitten by a mosquito and the parasite getting to the liver).It is why the vaccine is ‘only’ 40% effective. However, this is still a remarkable success and paves the way for the development of yet more potent vaccines.The vaccine, developed by the pharmaceutical giant GSK, is not going to replace all the other measures for controlling malaria such as insecticide-treated bed nets. It will be used alongside them to get closer to the goal of zero deaths from malaria.And it won’t be used outside of Africa where different forms of malaria, which the vaccine can’t protect against, are more prevalent.Dr Ashley Birkett, from the Path malaria vaccine initiative, said rolling out the vaccine was a “historic event” that would “take away fear” from families.He told me: “Imagine your young child could be healthy one day and full of potential and then after the bite of an infected mosquito, while playing with friends or sleeping in a bed, they could be dead in a couple of weeks.”Malaria is a huge problem, it’s frightening and scary.”Follow James on Twitter

Read more →

WHO recommends use of first proven malaria vaccine

The World Health Organization announced it is recommending the broad use of the first proven malaria vaccine.Produced by pharmaceutical giant GSK, it will be used to help children in Africa after pilots in three countries found it reduced cases by 40%.The head of the WHO Tedros Adhanom Ghebreyesus, who began his career as a malaria researcher, described the vaccine as a major breakthrough and a gift to the world.

Read more →

Weighing cancer cells to personalize drug choices

Researchers at MIT and Dana-Farber Cancer Institute have developed a new way to determine whether individual patients will respond to a specific cancer drug or not. This kind of test could help doctors to choose alternative therapies for patients who don’t respond to the therapies normally used to treat their cancer.
The new technique, which involves removing tumor cells from patients, treating the cells with a drug, and then measuring changes in the cells’ mass, could be applied to a wide variety of cancers and drug treatments, says Scott Manalis, the David H. Koch Professor of Engineering in the departments of Biological Engineering and Mechanical Engineering, and a member of the Koch Institute for Integrative Cancer Research.
“Essentially all of the clinically used cancer drugs either directly or indirectly stop the growth of cancer cells,” Manalis says. “That’s why we think measuring mass could offer a universal readout of the effects of a lot of different types of drug mechanisms.”
The new study, which focused on glioblastoma, an aggressive form of brain cancer, is part of a collaboration between the Koch Institute and Dana-Farber Precision Medicine programs to find new biomarkers and diagnostic tests for cancer.
Manalis and Keith Ligon, director of the Center for Patient Derived Models at Dana-Farber and an associate professor at Harvard Medical School, are the senior authors of the study, which appears today in Cell Reports. The lead authors of the paper are Max Stockslager SM ’17, PhD ’20 and Dana-Farber research technician Seth Malinowski.
Measuring cancer cells
Glioblastoma, which is diagnosed in about 13,000 Americans per year, is incurable, but radiation and drug treatment can help to prolong patients’ expected lifespan. Most do not survive longer than one to two years.

Read more →

Toxic fatty acids to blame for brain cell death after injury

Cells that normally nourish healthy brain cells called neurons release toxic fatty acids after neurons are damaged, a new study in rodents shows. This phenomenon is likely the driving factor behind most, if not all, diseases that affect brain function, as well as the natural breakdown of brain cells seen in aging, researchers say.
Previous research has pointed to astrocytes — a star-shaped glial cell of the central nervous system — as the culprits behind cell death seen in Parkinson’s disease and dementia, among other neurodegenerative diseases. While many experts believed that these cells released a neuron-killing molecule to “clear away” damaged brain cells, the identity of this toxin has until now remained a mystery.
Led by researchers at NYU Grossman School of Medicine, the new investigation provides what they say is the first evidence that tissue damage prompts astrocytes to produce two kinds of fats, long-chain saturated free fatty acids and phosphatidylcholines. These fats then trigger cell death in damaged neurons, the electrically active cells that send messages throughout nerve tissue.
Publishing Oct. 6 in the journal Nature, the study also showed that when researchers blocked fatty acid formation in mice, 75 percent of neurons survived compared with 10 percent when the fatty acids were allowed to form. The researchers’ earlier work showed that brain cells continued to function when shielded from astrocyte attacks.
“Our findings show that the toxic fatty acids produced by astrocytes play a critical role in brain cell death and provide a promising new target for treating, and perhaps even preventing, many neurodegenerative diseases,” says study co-senior author Shane Liddelow, PhD.
Liddelow, an assistant professor in the Department of Neuroscience and Physiology at NYU Langone Health, adds that targeting these fats instead of the cells that produce them may be a safer approach to treating neurodegenerative diseases because astrocytes feed nerve cells and clear away their waste. Stopping them from working altogether could interfere with healthy brain function.
Although it remains unclear why astrocytes produce these toxins, it is possible they evolved to destroy damaged cells before they can harm their neighbors, says Liddelow. He notes that while healthy cells are not harmed by the toxins, neurons become susceptible to the damaging effects when they are injured, mutated, or infected by prions, the contagious, misfolded proteins that play a major role in mad cow disease and similar illnesses. Perhaps in chronic diseases like dementia, this otherwise helpful process goes off track and becomes a problem, the study authors say.
For the investigation, researchers analyzed the molecules released by astrocytes collected from rodents. They also genetically engineered some groups of mice to prevent the normal production of the toxic fats and looked to see whether neuron death occurred after an acute injury.
“Our results provide what is likely the most detailed molecular map to date of how tissue damage leads to brain cell death, enabling researchers to better understand why neurons die in all kinds of diseases,” says Liddelow, also an assistant professor in the Department of Ophthalmology at NYU Langone.
Liddelow cautions that while the findings are promising, the genetic techniques used to block the enzyme that produces toxic fatty acids in mice are not ready for use in humans. As a result, the researchers next plan is to explore safe and effective ways to interfere with the release of the toxins in human patients. Liddelow and his colleagues had previously shown these neurotoxic astrocytes in the brains of patients with Parkinson’s, Huntington’s disease, and multiple sclerosis, among other diseases.
Funding for the study was provided by National Institutes of Health grants P30 CA124435, S10 RR027425, UL1 TR002529, and P30 CA023168. Further funding support was provided by the Cure Alzheimer’s Fund, The Blas Frangione Foundation, the U.S. Department of Defense, the Purdue Integrative Data Science Institute award, the Stark Neurosciences Research Institute, the Indiana Alzheimer Disease Center, and Eli Lilly. Liddelow maintains a financial interest in AstronauTx Ltd, a company targeting astrocytes as a possible treatment target for Alzheimer’s disease. The terms and conditions are being managed in accordance with the policies of NYU Langone.
In addition to Liddelow, other NYU Langone investigators involved in the study included Philip Hasel, PhD, and Uriel Rufen-Blanchette. Other study authors were first author Kevin Guttenplan, PhD; Maya Weigel, BA; Aaron Gilter, PhD; and co-senior author Ben Barres, MD, PhD; at Stanford University in Palo Alto, Calif.; Priya Prakash, PhD; Prageeth Wijewardhane; Jonathan Fine, PhD; and Guarav Chopra, PhD, at Purdue University in West Lafayette, Ind.; and Mikaela Neal, BS, and Kimberley Bruce, PhD, at the University of Colorado in Aurora.

Read more →