
Streeting begins talks to halt junior doctor strike

20 minutes agoBy
Read more →
20 minutes agoBy
Read more →
In a report, the regulator sharply criticized pharmacy benefit managers, a reversal from its longstanding hands-off approach to policing the companies.The Federal Trade Commission on Tuesday sharply criticized pharmacy benefit managers, saying in a scathing 71-page report that “these powerful middlemen may be profiting by inflating drug costs and squeezing Main Street pharmacies.”The regulator’s study signals a significant ramping up of its scrutiny of benefit managers under the agency’s chair, Lina Khan. It represents a remarkable turnabout for an agency that has long taken a hands-off approach to policing these companies.The F.T.C. has so far stopped short of bringing a lawsuit or other enforcement action against a benefit manager. But the industry fears that the report could lead to a formal investigation into its practices or to a lawsuit accusing benefit managers of anticompetitive conduct. The agency’s findings could also fuel legislative efforts in Congress and in the states to impose limits on the industry.The three largest benefit managers — CVS Health’s Caremark, Cigna’s Express Scripts and UnitedHealth Group’s Optum Rx — collectively process roughly 80 percent of prescriptions in the United States. Hired by employers and government health insurance programs like Medicare, benefit managers are responsible for negotiating prices with drug makers, paying pharmacies and helping decide which drugs are available and at what cost to patients.Benefit managers are supposed to save everyone money. But in recent years, the industry has grown more consolidated and has taken more control over how patients get their medicines, in a shift that critics say contributes to driving up drug costs.We are having trouble retrieving the article content.Please enable JavaScript in your browser settings.Thank you for your patience while we verify access. If you are in Reader mode please exit and log into your Times account, or subscribe for all of The Times.Thank you for your patience while we verify access.Already a subscriber? Log in.Want all of The Times? Subscribe.
Read more →
She was involved in a minor car accident three months earlier. Could that somehow be the cause?“I feel just horrible, and no one knows what to do,” the 21-year-old woman sobbed to her father. In one hand, she held her phone, in the other, a red Solo cup. The pungent smell from the vomit-filled cup wafted through the room. Despite her best efforts, the strange lightness she felt when standing told her that she was dehydrated. And why wouldn’t she be? Everything she ate or drank came back minutes later in terrible heaves that tore at the aching muscles in her chest and abdomen. She filled the cup more than once during this call with her father. And maybe a dozen times earlier that day. And the day before. And the day before that.She paced around the room as she listened to her father. “You need to go to the emergency room,” he told her. She didn’t want to go. She already went seven times over the past three months since this vomiting became part of her daily routine. Most of the time they just gave her IV fluids and sent her home. They thought it was her anxiety. She was admitted twice. Both times they ran countless tests, then sent her home to vomit there — without any answers. Nevertheless, the woman took her father’s advice, and her roommate drove her to the Emory University Hospital emergency room in Atlanta. After getting some IV fluids and the anti-emetic Zofran, which hadn’t helped her in the past, she was discharged. She called her father as soon as she got back to her apartment, and he told her to come home to Cleveland. It was the week before Thanksgiving, and lots of flights were full, but she finally found one for that afternoon and packed her bag.Sideswiped and WhipsawedJust days after arriving in Atlanta that August to start her junior year at Emory University, she was in a car accident. Another car made an illegal turn and sideswiped hers, and she whipsawed against the door. She felt fine, though, and after they exchanged insurance information, she just went on with her day. But by the next day, she had started throwing up. Everything she ate or drank caused her to retch and vomit. She went to the E.R. Because the vomiting started right after her accident, the emergency-department doctor thought she had a concussion. He gave her some fluids and a medicine to stop the nausea. It should get better in a couple of days, he assured her. But it didn’t. She’d been vomiting every day since then. She felt fine until she ate or drank something — anything. Then, within minutes, she would have an overwhelming sense of nausea, and the wrenching spasms and vomiting would start. The flight to Cleveland was quick. Her father picked her up at the airport and drove directly to the Cleveland Clinic Children’s hospital. Her regular doctor, Ellen Rome, the head of the Center for Adolescent Medicine there, wasn’t in the office that holiday week but arranged for the young woman to see a pediatric gastroenterologist. She immediately admitted her to the hospital. The doctor who admitted her that night considered the possible causes of this kind of unremitting vomiting. The patient was taking medications for anxiety, so maybe the doctors in Atlanta were right — maybe this was psychogenic vomiting, caused by her longstanding psychiatric disorder. But there were other possibilities. Regular marijuana use could cause persistent vomiting. Hyperemesis gravidarum — excessive vomiting in pregnancy — was also possible. Those were easy to test for. Hyperthyroidism can cause this kind of vomiting as well. By the next morning results from the testing began to trickle in. She was not pregnant and had no evidence of marijuana in her system. Her thyroid was normal. So were the rest of the more routine studies.We are having trouble retrieving the article content.Please enable JavaScript in your browser settings.Thank you for your patience while we verify access. If you are in Reader mode please exit and log into your Times account, or subscribe for all of The Times.Thank you for your patience while we verify access.Already a subscriber? Log in.Want all of The Times? Subscribe.
Read more →
The nervous energy was palpable as hundreds of bike riders, shrink-wrapped in colorful Lycra outfits, waited for the start of the 50-mile Half-Century ride from the Santa Fe Railyard, a center for art galleries, restaurants and a weekly farmers’ market in Santa Fe, N.M. Then, at last, we were winding through town as eight police officers on motorcycles leapfrogged ahead to guard the intersections.We rode past the Roundhouse, where the New Mexico Legislature meets. We passed Museum Hill, where four museums explore the Native American Southwest, the Spanish colonial past and more. Then, finally, after a dozen or so miles, Santa Fe was far behind us and we were on our own, riding through rolling ranch land.The Half-Century ride takes cyclists through rolling ranchland and a vast, high-desert landscape.Kate Russell for The New York TimesIt was the second day of a two-day biking event that each spring attracts more than 1,500 participants, who come for the companionship and the challenge to ride together through a high-desert landscape rich in history, art and Indigenous traditions. Of all those who had showed up for the Half-Century trek, I was the only one on a handcycle.Handcycles allow riders to sit or lie on their backs, turn cranks with their hands and propel themselves with arm power instead of leg power. My handcycle, a lightweight Swedish model, was equipped with an electric assist motor — essential for people like me who can’t move their legs.My arms were going to feel itTwelve years ago, while leading a climb in Joshua Tree National Park in Southern California, I made a costly mistake and plunged 40 feet onto the unforgiving rock. The fall burst my spine and severed my spinal cord, leaving me a paraplegic.We are having trouble retrieving the article content.Please enable JavaScript in your browser settings.Thank you for your patience while we verify access. If you are in Reader mode please exit and log into your Times account, or subscribe for all of The Times.Thank you for your patience while we verify access.Already a subscriber? Log in.Want all of The Times? Subscribe.
Read more →
8 hours agoBy
Read more →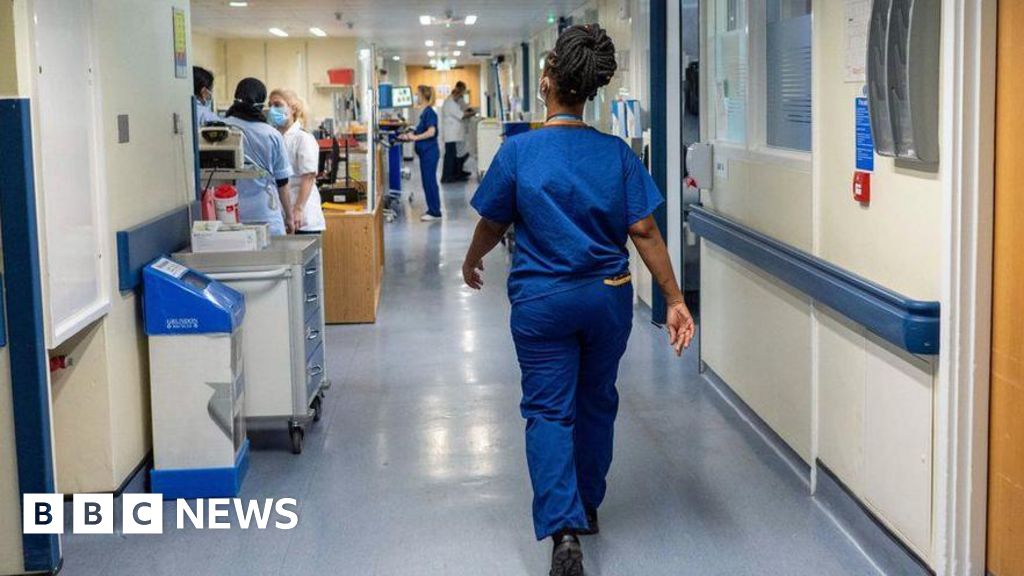
There is shocking bullying, racism and incompetence in the organisation responsible for ensuring NHS nurses and midwives in the UK are safe to have around patients, a damning report says.
Read more →
A New York Times mental health reporter wants to hear why therapy didn’t work out.People who have benefited from mental health therapy often praise its upsides, which can include developing better coping skills, stronger relationships and a calmer mind.But what happens when a therapist just isn’t helping, or is actually causing harm? A psychologist may send up red flags for a client by yawning during sessions, running late every week or giving bad advice.Patients can report unethical behavior to a counselor’s state licensing board, but there isn’t always a recourse for someone who feels as though a therapist has been poorly trained or is inexperienced or just bad at the job. At this time, there is no federal agency responsible for regulating psychotherapy.Have you ever signed up for therapy but quit after ineffective or even offensive treatment? We want to hear from you. If you do reach out, a reporter may be in contact for permission to share your story in an upcoming article.Tell us what happened
Read more →
An expert on Parkinson’s disease from Walter Reed National Military Medical Center visited the White House eight times in eight months from last summer through this spring, including at least once for a meeting with President Biden’s physician, according to official visitor logs.The expert, Dr. Kevin Cannard, is a neurologist who specializes in movement disorders and recently published a paper on Parkinson’s. The logs, released by the White House in response to a request from The New York Times, document visits from July 2023 through March of this year. More recent visits, if there have been any, would not be released until later under the White House’s voluntary disclosure policy.It was unclear whether Dr. Cannard was at the White House to consult specifically about the president or whether he was there as part of unrelatedfc meetings with the White House medical team. Dr. Cannard’s LinkedIn page describes him as “supporting the White House Medical Unit” for more than 12 years, which would include during the administrations of Presidents Donald J. Trump and Barack Obama.Dr. Cannard did not respond to repeated requests for comment. The White House did not comment specifically on the purpose of his visits. “A wide variety of specialists from the Walter Reed system visit the White House complex to treat the thousands of military personnel who work on the grounds,” Andrew Bates, a White House spokesman, said in a statement.Mr. Bates said that the president “has been seen by a neurologist once a year” as part of his overall annual physical checkup and “that examination has found no sign of Parkinson’s and he is not being treated for it.” He declined to provide dates of any meetings between Mr. Biden and any of his specialists but said “there have been no neurologist visits besides the one for his physical per year, three in total.”Dr. Cannard met on Jan. 17 with Dr. Kevin O’Connor, the White House physician, as well as Dr. John Atwood, a cardiologist at Walter Reed, and another person in the early evening in the White House residence clinic, the logs showed. That meeting came a month before Mr. Biden underwent his most recent annual physical checkup at Walter Reed on Feb. 28.We are having trouble retrieving the article content.Please enable JavaScript in your browser settings.Thank you for your patience while we verify access. If you are in Reader mode please exit and log into your Times account, or subscribe for all of The Times.Thank you for your patience while we verify access.Already a subscriber? Log in.Want all of The Times? Subscribe.
Read more →
The research, which builds on previous work, eventually may lead to a more objective diagnostic tool, scientists said.The process for diagnosing a child with autism heavily relies on a parent’s description of their child’s behavior and a professional’s observations. It leaves plenty of room for human error.Parents’ concerns may skew how they answer questionnaires. Providers may hold biases, leading them to underdiagnose certain groups. Children may show widely varying symptoms, depending on factors like culture and gender.A study published Monday in Nature Microbiology bolsters a growing body of research that suggests an unlikely path to more objective autism diagnoses: the gut microbiome.After analyzing more than 1,600 stool samples from children ages 1 to 13, researchers found several distinct biological “markers” in the samples of autistic children. Unique traces of gut bacteria, fungi, viruses and more could one day be the basis of a diagnostic tool, said Qi Su, a researcher at the Chinese University of Hong Kong and the author of the study.A tool based on biomarkers could help professionals diagnose autism sooner, giving children access to treatments that are more effective at a younger age, he said.“Too much is left to questionnaires,” said Sarkis Mazmanian, a microbiome researcher at the California Institute of Technology. “If we can get to something we can measure — whatever it is — that’s a huge improvement.”We are having trouble retrieving the article content.Please enable JavaScript in your browser settings.Thank you for your patience while we verify access. If you are in Reader mode please exit and log into your Times account, or subscribe for all of The Times.Thank you for your patience while we verify access.Already a subscriber? Log in.Want all of The Times? Subscribe.
Read more →
A multidisciplinary research team has developed a discovery platform to probe the function of genes involved in metabolism — the sum of all life-sustaining chemical reactions.
The investigators used the new platform, called GeneMAP (Gene-Metabolite Association Prediction), to identify a gene necessary for mitochondrial choline transport. The resource and derived findings were published July 8 in the journal Nature Genetics.
“We sought to gain insight into a fundamental question: ‘How does genetic variation determine our “chemical individuality” — the inherited differences that make us biochemically unique?” said Eric Gamazon, PhD, associate professor of Medicine in the Division of Genetic Medicine at Vanderbilt University Medical Center. Gamazon is the senior and co-corresponding author of the study with Kivanç Birsoy, PhD, of The Rockefeller University.
Metabolic reactions play critical roles in nutrient absorption, energy production, waste disposal, and synthesis of cellular building blocks including proteins, lipids and nucleic acids. About 20% of protein-coding genes are dedicated to metabolism, including genes that code for small-molecule transporters and enzymes, Gamazon said.
Abnormalities in metabolic functions are associated with a range of disorders including neurodegenerative diseases and cancers.
“Despite decades of research, many metabolic genes still lack known molecular substrates. The challenge is in part due to the enormous structural and functional diversity of the proteins,” Gamazon said.
To discover functions for “orphan” transporters and enzymes — proteins with unknown substrates — the researchers developed the GeneMAP discovery platform. They used datasets from two independent large-scale human metabolome genome-wide/transcriptome-wide association studies and demonstrated with in silico validation that GeneMAP can identify known gene-metabolite associations and discover new ones. In addition, they showed that GeneMAP-derived metabolic networks can be used to infer the biochemical identity of uncharacterized metabolites.
To experimentally validate new gene-metabolite associations, the researchers selected their top finding (SLC25A48-choline) and performed in vitro biochemical studies. SLC25A48 is a mitochondrial transporter that did not have a defined substrate for transport. Choline is an essential nutrient used in multiple metabolic reactions and in the synthesis of cell membrane lipids.
The researchers showed that SLC25A48 is a genetic determinant of plasma choline levels. They further conducted radioactive mitochondrial choline uptake assays and isotope tracing experiments to demonstrate that loss of SLC25A48 impairs mitochondrial choline transport and synthesis of the choline downstream metabolite betaine.
They also investigated the consequences of the relationship between SLC25A48 and choline on the human medical phenome (symptoms, traits and diseases listed in electronic health records) using large-scale biobanks (UK Biobank and BioVU). They identified eight disease associations.
“What’s exciting about this study is its interdisciplinarity — the combination of genomics and metabolism to identify a long-sought mitochondrial choline transporter,” Gamazon said. “We think, given the extensive in silico validation studies in independent datasets and the proof-of-principle experimental studies, our approach can help identify the substrates of a wide range of enzymes and transporters, and ‘deorphanize’ these metabolic proteins.”
Birsoy is Chapman-Perelman Associate Professor, Head of the Laboratory of Metabolic Regulation and Genetics at The Rockefeller University, and a Searle and Pew-Stewart Scholar. Co-authors of the study include Artem Khan, Gokhan Unlu, PhD, (who completed his doctoral degree at Vanderbilt), Yuyang Liu, Ece Kilic and Timothy Kenny, PhD, at Rockefeller, and Phillip Lin at VUMC.
The research was supported by the National Institutes of Health (grants F99CA284249, F32DK127836, R01DK123323, R01HG011138, R01GM140287, R56AG068026, U24OD035523, R35HG010718), Boehringer Ingelheim Fonds PhD Fellowship, and Damon Runyon Cancer Research Foundation.