Breakthrough in glioblastoma treatment with the help of a virus

In a recently published manuscript, Howard Colman, MD, PhD, Jon M. Huntsman Presidential Professor of Neuro-Oncology and co-leader of the Neurologic Cancers Disease Center and the Experimental Therapeutics CCSG program at Huntsman Cancer Institute, identified a potential breakthrough in glioblastoma treatment.
Glioblastoma, or GBM, is an aggressive type of brain cancer. According to Colman, this is the most common type of cancerous brain tumor in adults. Standard treatments include radiation and chemotherapy. Unfortunately, typical GBM tumors are often resistant to these treatments and only respond for a matter of months. Due to the aggressive nature of this cancer, tumors often recur and spread.
“Typically, when patients have a recurrence of GBM, and you put them on a new drug, the tumor only stays in check for one to two months,” says Colman. “We are constantly looking for better treatments and doing clinical trials to try and identify new ways to help our patients with GBM.”
Currently in phase 2, this clinical trial tested the use of two experimental agents for glioblastoma — a novel viral therapy and a drug that activates the immune system. This specific immunotherapy, called a checkpoint inhibitor, blocks proteins made by cancer cells that help them hide from a patient’s own immune system. While immunotherapy uses a patient’s immune system to help fight cancer growth and has been successful in other cancer types, these drugs generally have not been effective when used alone in GBM treatment. This is where the viral therapy comes in.
Using a modified virus normally responsible for minor infections and the common cold, researchers created a treatment that specifically attacks tumor cells, while leaving normal cells intact.
Clinicians inject the virus directly into the patient’s tumor, and the patient receives the checkpoint inhibitor called pembrolizumab through an IV on a recurring schedule.
“The idea here is that the virus kills some of the tumor cells and the dying tumor cells then help turn on the patient’s immune system,” says Colman. “We then give the patient a checkpoint inhibitor, which further activates the immune system’s response against the tumor. This is potentially a significant advance, as GBM does not typically respond to immunotherapy.”
During the initial phase, researchers focused on finding the correct dose and assessing safety of both agents. In phase 2, they looked at the percentage of patients who saw improvement in the size of their tumor, delay in progression of tumor, and overall survival.
Around 10% of patients enrolled in this trial experienced tumor shrinkage, with two tumors demonstrating a complete response. Patients who experienced shrinkage also appeared to have delayed tumor growth and lived much longer than expected.
“While this treatment appeared to only help a subset of patients in this trial, the hope is that we’ll be able to improve survival significantly for some GBM patients, while at the same time, working to try and find other effective therapies for patients where this combination doesn’t work,” says Colman.
This is full-circle moment for Colman, who worked on the early stages of the modifying the virus during his time at MD Anderson from 2002-2010.
Huntsman Cancer Institute accrued many patients for this trial and plans to continue to work on the future development of this combination therapy for GBM, as well as many other experimental treatments currently in clinical trials.

Read more →

England Limits Use of Puberty-Blocking Drugs to Research Only

The NewsThe National Health Service of England announced on Friday that it would limit the use of puberty-suppressing drugs to children enrolled in clinical trials. The change comes as the agency’s pediatric gender services have struggled to keep up with soaring demand.A document explaining the agency’s reasoning stated that “there is not enough evidence to support their safety or clinical effectiveness as a routinely available treatment.”The N.H.S. had released a draft of this policy change in October, but Friday’s announcement formally instituted the new approach after months of public comment. The policy will go into effect later this year.The N.H.S. announced last year it would shut down the Tavistock Gender Identity Development Service in London after the clinic saw a sharp rise of referrals.Peter Nicholls/ReutersWhy It Matters: Other countries have limited the drugs, tooThe change is part of a broader push in several countries to limit gender-related medical treatments for young people.After conducting evidence reviews, Finland has begun limiting who can access gender-related treatments and Sweden has restricted the use of puberty blockers and hormones to clinical trials. A Norwegian health body and the French National Academy of Medicine have also urged caution.In the United States, more than 20 Republican-led states have passed laws banning the use of puberty-blocking drugs and hormones, with some making it a felony for doctors to prescribe them. Hundreds of clinicians across the country — including some who have raised concerns about which adolescents should receive gender-related treatments — have denounced the bans, saying such decisions should be made by patients, their families and their doctors.Background: Data on the effect of blockers is sparseLast year, N.H.S. England announced that it would be shutting down the country’s only youth gender clinic after an external review showed that the Tavistock Gender Identity Development Service had been unable to provide appropriate care for the rapidly increasing number of adolescents seeking gender treatments. The clinic had seen a sharp rise in referrals, from 250 young people in 2011 to 5,000 in 2021.Puberty blockers, which work by suppressing estrogen and testosterone, were first tested on children with gender dysphoria in the Netherlands in the 1990s. The Dutch researchers published their first study on 70 children in 2011, finding that the adolescents reported a decrease in depression and anxiety after taking the drugs.But a British study of Tavistock patients published in 2021 showed that blockers had no effect on children’s scores on psychological tests. The study found that 43 out of the 44 participants later chose to start testosterone or estrogen treatments. One interpretation of the data is that all were good candidates for hormone therapy. But the numbers raised concerns at the N.H.S. about whether the drugs served their intended purpose of giving adolescents time to think.“The most difficult question is whether puberty blockers do indeed provide valuable time for children and young people to consider their options, or whether they effectively ‘lock in’ children and young people to a treatment pathway,” Dr. Hilary Cass, the pediatrician overseeing the independent review of the N.H.S. gender service, wrote last year.What’s Next: England will start a trial of children taking blockersThe N.H.S. is organizing a clinical trial for all children receiving puberty blockers from the health service, which it expects will begin enrollment in 2024.Although the Tavistock clinic has been closed, regional centers are opening across Britain to expand gender-related services for young people. The N.H.S. said that the new system for treating minors with gender-related issues will establish standardized assessments and incorporate much more mental health support.“The main objective is to alleviate distress associated with gender incongruence and promote the individual’s global functioning and well-being,” the N.H.S. guidance said.

Read more →

Mother jailed for taking abortion pills after legal limit

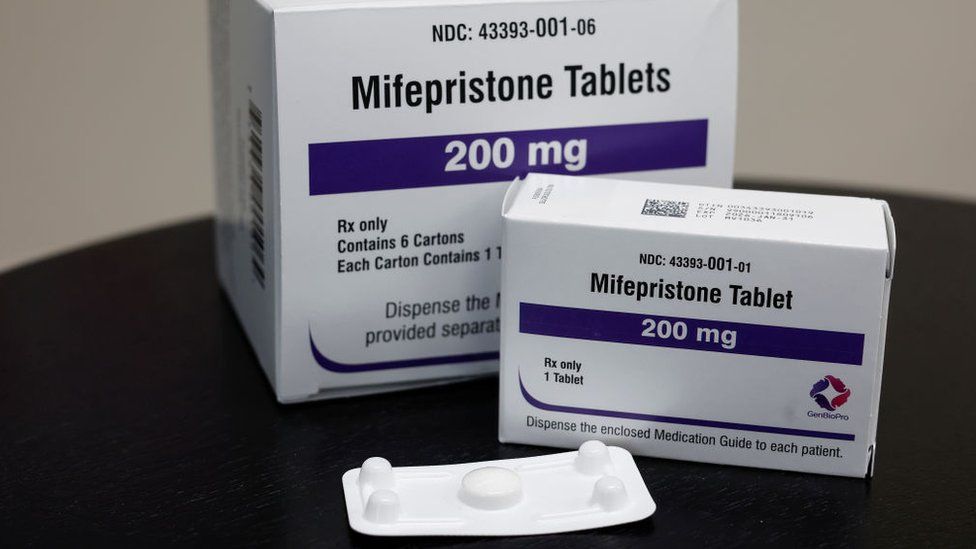
Published3 minutes agoShareclose panelShare pageCopy linkAbout sharingImage source, Getty ImagesBy Riyah Collins & PA MediaBBC News, West MidlandsA mother-of-three has been jailed for more than two years for inducing an abortion after the legal limit.The 44-year-old received the medication following a remote consultation where she was not honest about how far along she was in her pregnancy.The “pills by post” scheme, introduced in lockdown, was to be used for unwanted pregnancies up to 10 weeks.However, Stoke-on-Trent Crown Court heard the woman was between 32-34 weeks pregnant when she took them.Abortion is legal up to 24 weeks. However, after 10 weeks the procedure is carried out in a clinic.Prosecutors argued the woman, who the BBC is not naming, had provided false information knowing she was over the time limit and had made online searches which they said indicated “careful planning”.The court heard between February and May 2020 she had searched “how to hide a pregnancy bump”, “how to have an abortion without going to the doctor” and “how to lose a baby at six months”.Based on the information she provided the British Pregnancy Advisory Service (BPAS), she was sent the tablets because it was estimated she was seven weeks pregnant.Image source, Getty ImagesOn 11 May 2020, having taken the pills, an emergency call was made at 18:39 BST saying she was in labour.The baby was born not breathing during the phonecall and was confirmed dead about 45 minutes later. A post-mortem examination recorded the baby girl’s cause of death as stillbirth and maternal use of abortion drugs and she was estimated to be between 32 and 34 weeks’ gestation.If you have been affected by the issues raised in this article, help and support is available via BBC Action LineThe woman, from Staffordshire, already had three sons before she became pregnant again in 2019.The court heard she had moved back in with her estranged husband at the start of lockdown while carrying another man’s baby.The judge accepted she was “in emotional turmoil” as she sought to hide the pregnancy.The woman was initially charged with child destruction, which she denied.She later pleaded guilty to an alternative charge of section 58 of the Offences Against the Person Act 1861, administering drugs or using instruments to procure abortion, which was accepted by the prosecution.Leniency letter ‘not appropriate’Sentencing, judge Mr Justice Edward Pepperall said it was a “tragic” case, adding that if she had pleaded guilty earlier he may have been able to consider suspending her jail sentence.He said the woman was “wracked by guilt” and had suffered depression and said she was a good mother to three children, one of whom has special needs, who would suffer from her imprisonment.She received a 28-month sentence, 14 of which will be spent in custody with the remainder on licence.Ahead of Monday’s hearing, a letter co-signed by a number of women’s health organisations was sent to the court calling for a non-custodial sentence.However, the judge said it was “not appropriate” and that his duty was “to apply the law as provided by Parliament”.He told the defendant the letter’s authors were “concerned that your imprisonment might deter other women from accessing telemedical abortion services and other late-gestation women from seeking medical care or from being open and honest with medical professionals”.But he said it also “has the capacity to be seen as special pleading by those who favour wider access to abortions and is, in my judgment, just as inappropriate as it would be for a judge to receive a letter from one of the groups campaigning for more restrictive laws”.’Archaic law’The sentencing has sparked outcry among women’s rights organisations and campaigners.BPAS said it was “shocked and appalled” by the woman’s sentence which they said was based on an “archaic law”.”No woman can ever go through this again,” said its chief executive, Clare Murphy. “Over the last three years, there has been an increase in the numbers of women and girls facing the trauma of lengthy police investigations and threatened with up to life imprisonment under our archaic abortion law,” she said.”Vulnerable women in the most incredibly difficult of circumstances deserve more from our legal system.”She said MPs must do more to offer protection so “no more women in these desperate circumstances are threatened with prison again”.Image source, ParliamentLabour MP Stella Creasy called for “urgent reform”.”The average prison sentence for a violent offence in England is 18 months,” she said in a tweet. “A woman who had an abortion without following correct procedures just got 28 months under an 1868 act – we need urgent reform to make safe access for all women in England, Scotland and Wales a human right.”When asked whether the prime minister was confident criminalising abortion in some circumstances was the right approach, Rishi Sunak’s official spokesperson said the current laws struck a balance.”Our laws as they stand balance a woman’s right to access safe and legal abortions with the rights of an unborn child,” he said.”I’m not aware of any plans to address that approach.”Follow BBC West Midlands on Facebook, Twitter and Instagram. Send your story ideas to: newsonline.westmidlands@bbc.co.ukRelated Internet LinksHM Courts & Tribunals ServiceBritish Pregnancy Advisory ServiceThe BBC is not responsible for the content of external sites.

Read more →

Chronic exposure to lead, cadmium and arsenic increases risk of cardiovascular disease

Chronic exposure to low levels of lead, cadmium and arsenic through commonly used household items, air, water, soil and food is associated with an increased risk of cardiovascular disease, according to a new American Heart Association scientific statement published today in the Journal of the American Heart Association, an open access, peer-reviewed journal of the American Heart Association.
This scientific statement reviews evidence linking chronic exposure to low or moderate levels of three contaminant metals — lead, cadmium and arsenic — to cardiovascular diseases including coronary artery disease, stroke and peripheral artery disease. It highlights clinical and public health implications. Traditional risk factors for cardiovascular disease do not currently include environmental toxicants. The field of environmental cardiology identifies exposure to pollutants including contaminant metals as modifiable risks for cardiovascular disease.
“Large population studies indicate that even low-level exposure to contaminant metals is near-universal and contributes to the burden of cardiovascular disease, especially heart attacks, stroke, disease of the arteries to the legs and premature death from cardiac causes,” said Gervasio A. Lamas, M.D., FAHA, chair of the statement writing group and chairman of medicine and chief of the Columbia University Division of Cardiology at Mount Sinai Medical Center in Miami Beach, Florida.
“These metals interfere with essential biological functions and affect most populations on a global scale,” said vice chair of the statement writing group Ana Navas-Acien, M.D., Ph.D., a professor of environmental health sciences at Columbia University’s Mailman School of Public Health and the director of the Columbia University Northern Plains Superfund Research Program in New York City. “After exposure, lead and cadmium accumulate in the body and remain in bones and organs for decades. In the U.S. alone, one large study suggested that more than 450,000 deaths annually could be attributed to lead exposure.”
Where are people exposed to contaminant metals?
Exposure to contaminant metals most often occurs involuntarily, through activities of daily living. Lead may be found in a variety of items such as paint in old homes (lead paint was banned in the U.S. in 1978), tobacco products, second-hand smoke, contaminated foods (ground water and some pottery, ceramics and kitchenware are sources of lead contamination in food), water pipes, spices, cosmetics, electronics and industrial emissions. Cigarette smoking is a source of both lead and cadmium.

Cadmium is found in nickel-cadmium batteries, pigments, plastic, ceramics and glassware, and construction products. Industrially produced fertilizers use phosphate rock that is naturally rich in cadmium, which then contaminates root vegetables and leafy green plants (including tobacco).
Arsenic exposure is primarily through groundwater, which affects drinking water, soil and food grown in contaminated soil. Notably, arsenic builds up in rice more than other food crops.
While exposure and risk occur across diverse populations regardless of socioeconomic level, some people experience greater exposure to toxic metals, according to the statement. Risk of exposure is higher for people who live closer to major roadways, industrial sources and hazardous waste sites; reside in older houses; or in areas where environmental regulations are poorly enforced and responses to community complaints are inadequate.
“This is a global issue in which lower-income communities are disproportionately exposed to toxic metals through contaminated air, water and soil,” said Navas-Acien. “Addressing metal exposure in these populations may provide a strategy to reduce cardiovascular disease disparities and advance environmental justice.”
What are the cardiovascular risks of contaminant metals?
The scientific statement outlines global epidemiologic research confirming that lead, cadmium and arsenic are associated with premature death, due in large part to increased cardiovascular disease risk. The global research includes: A 2021 American Heart Association scientific statement recognized exposure to toxic metals as a non-conventional risk factor for peripheral artery disease. A 2018 review published in the British Medical Journal assessed 37 studies representing nearly 350,000 people from more than a dozen countries. The review reported that higher urine levels of arsenic and blood levels of lead and cadmium were associated with 15%-85% higher risk for stroke and heart disease. One study in China found that higher levels of lead in the blood were associated with carotid plaque in people with Type 2 diabetes. Another found that cadmium and arsenic were associated with a higher rate of heart disease and ischemic stroke. In Spain, a general population study found that cadmium in urine was associated with increased rates of newly diagnosed cardiovascular disease.

What can be done about metals in the environment?
Monitoring environmental metal levels and testing for metal in individuals are key steps to implement appropriate public health initiatives, the writing group suggests. Lead levels in children with symptoms of exposure are monitored by health professionals using blood tests. However, there are no monitoring guidelines or exposure limits established for contaminant metals in adults other than those required for specific types of work. Future research is needed to establish if such testing may be an effective strategy to identify and protect people at risk of cardiovascular disease.
The statement authors note that decreasing metal exposure in tobacco, protecting community water systems and wells, and minimizing metal contamination in air, food and soil are all examples of public health measures that may reduce exposure to metals.
“Cardiovascular health may be improved with a multi-pronged approach that recognizes environmental cardiology and includes environmental monitoring and biomonitoring of contaminant metals; controlling for sources of exposure; and developing clinical interventions that remove metals or weaken their effects on the body,” said Lamas, who is also a professor of medicine at Columbia University Irving Medical Center in New York City.
While there is currently no standard medical therapy to counteract the vascular impact of contaminant metals, there is research in progress to address the potential for treating individuals for exposure. Some research is assessing the effect of chelating agents, which are medications that can remove contaminant metals, especially lead and cadmium, from the body. The chelating agent binds to metals so they can be excreted. In addition, the statement suggests research is needed to investigate nutritional supplements that may reduce the effects of contaminant metals and accelerate excretion. Supplements that have shown potential based on small trials include folate and N-acetyl cysteine.
This scientific statement was prepared by the volunteer writing group on behalf of the American Heart Association’s Council on Epidemiology and Prevention; the Council on Cardiovascular and Stroke Nursing; the Council on Lifestyle and Cardiometabolic Health; the Council on Peripheral Vascular Disease; and the Council on Kidney in Cardiovascular Disease. American Heart Association scientific statements promote greater awareness about cardiovascular diseases and stroke issues and help facilitate informed health care decisions. Scientific statements outline what is currently known about a topic and what areas need additional research. While scientific statements inform the development of guidelines, they do not make treatment recommendations. American Heart Association guidelines provide the Association’s official clinical practice recommendations.
The Association receives funding primarily from individuals. Foundations and corporations (including pharmaceutical, device manufacturers and other companies) also make donations and fund specific Association programs and events. The Association has strict policies to prevent these relationships from influencing the science content. Revenues from pharmaceutical and biotech companies, device manufacturers and health insurance providers, and the Association’s overall financial information are available here.

Read more →

New study links contraceptive pills and depression

In a global perspective, depression is the leading cause of ill health and disability. More than 264 million people are affected and at least 25 per cent of all women and 15 per cent of all men experience a depression that requires treatment at some point during their life.
The possibility that contraceptive pills might have negative effects on mental health and even lead to depression has long been discussed. Although many women choose to stop using contraceptive pills because of the influence on their mood, until now the picture emerging from research has not been straightforward. This study is one of the largest and widest-ranging to date, following more than a quarter of a million women from UK Biobank from birth to menopause.
The researchers collected data about women’s use of contraceptive pills, the time at which they were first diagnosed with depression and when they first experienced symptoms of depression without receiving a diagnosis. The method of contraception studied was combined contraceptive pills, which contain progestogen, a compound resembling the hormone progesterone, and oestrogen. Progestogen prevents ovulation and thickens the cervical mucus to prevent sperms from entering the uterus, while oestrogen thins the uterine lining to hinder the implantation of a fertilised egg.
“Although contraception has many advantages for women, both medical practitioners and patients should be informed about the side-effects identified in this and previous research,” says Therese Johansson of the Department of Immunology, Genetics and Pathology at Uppsala University, one of the researchers leading the study.
According to the study, women who began to use contraceptive pills as teenagers had a 130 per cent higher incidence of symptoms of depression, while the corresponding increase among adult users was 92 per cent.
“The powerful influence of contraceptive pills on teenagers can be ascribed to the hormonal changes caused by puberty. As women in that age group have already experienced substantial hormonal changes, they can be more receptive not only to hormonal changes but also to other life experiences,” Johansson says.
The researchers were also able to see that the increased incidence of depression declined when the women continued to use contraceptive pills after the first two years. However, teenage users of contraceptive pills still had an increased incidence of depression even after stopping using the pill, which was not observed in adult users of contraceptive pills.
“It is important to emphasise that most women tolerate external hormones well, without experiencing negative effects on their mood, so combined contraceptive pills are an excellent option for many women. Contraceptive pills enable women to avoid unplanned pregnancies and they can also prevent illnesses that affect women, including ovarian cancer and uterine cancer. However, certain women may have an increased risk of depression after starting to use contraceptive pills.”
The findings of the study point to a need for healthcare professionals to be more aware of possible links between different systems in the body, such as depression and the use of contraceptive pills. The researchers conclude that it is important for care providers to inform women who are considering using contraceptive pills of the potential risk of depression as a side-effect of the medicine.
“Since we only investigated combined contraceptive pills in this study, we cannot draw conclusions about other contraceptive options, such as mini pills, contraceptive patches, hormonal spirals, vaginal rings or contraceptive rods. In a future study, we plan to examine different formulations and methods of administration. Our ambition in comparing different contraceptive methods is to give women even more information to help them take well-informed decisions about their contraceptive options,” Johansson says.

Read more →

New method enables study of nano-sized particles

Researchers at Karolinska Institutet have created a new method of studying the smallest bioparticles in the body. The study, which is published in Nature Biotechnology, has considerable scientific potential, such as in the development of more effective vaccines.
Circulating around the body are nanoparticles that affect it in one way or another. For example, there are lipoproteins that maintain cell metabolism, pathogenic viruses that cause many diseases and lipid nanoparticles that are used to carry drugs, like recent lipid nanoparticle-based mRNA vaccines.
However, such particles are too small to be studied easily. To enable this, the researchers in this study have developed a new method that they call single-particle profiling (SPP).
“We’re presenting a new method that gives unprecedented information about nano-sized particles,” says the study’s last author assistant professor Erdinc Sezgin at SciLifeLab and the Department of Women’s and Children’s Health, Karolinska Institutet.
The method makes it possible to measure the content and properties of thousands of particles between 5 and 200 nanometres in size.
“Our method can be used to study bioparticles in health and disease.” says Dr Sezgin. “Moreover, it will also be an invaluable tool in creating better and more effective nanocarriers.”
One of the researchers’ goals was to create a simple, inexpensive method accessible to all researchers.
“We established a method based on commercially available microscopes and made our data-analysis tool and all our data freely available,” says Dr Sezgin.

Read more →

How Chatbots Are Helping Doctors Be More Human and Empathetic

On Nov. 30 last year, Microsoft and OpenAI released the first free version of ChatGPT. Within 72 hours, doctors were using the artificial intelligence-powered chatbot.“I was excited and amazed but, to be honest, a little bit alarmed,” said Peter Lee, the corporate vice president for research and incubations at Microsoft.He and other experts expected that ChatGPT and other A.I.-driven large language models could take over mundane tasks that eat up hours of doctors’ time and contribute to burnout, like writing appeals to health insurers or summarizing patient notes.They worried, though, that artificial intelligence also offered a perhaps too tempting shortcut to finding diagnoses and medical information that may be incorrect or even fabricated, a frightening prospect in a field like medicine.Most surprising to Dr. Lee, though, was a use he had not anticipated — doctors were asking ChatGPT to help them communicate with patients in a more compassionate way.In one survey, 85 percent of patients reported that a doctor’s compassion was more important than waiting time or cost. In another survey, nearly three-quarters of respondents said they had gone to doctors who were not compassionate. And a study of doctors’ conversations with the families of dying patients found that many were not empathetic.Enter chatbots, which doctors are using to find words to break bad news and express concerns about a patient’s suffering, or to just more clearly explain medical recommendations.Even Dr. Lee of Microsoft said that was a bit disconcerting.“As a patient, I’d personally feel a little weird about it,” he said.But Dr. Michael Pignone, the chairman of the department of internal medicine at the University of Texas at Austin, has no qualms about the help he and other doctors on his staff got from ChatGPT to communicate regularly with patients.He explained the issue in doctor-speak: “We were running a project on improving treatments for alcohol use disorder. How do we engage patients who have not responded to behavioral interventions?”Or, as ChatGPT might respond if you asked it to translate that: How can doctors better help patients who are drinking too much alcohol but have not stopped after talking to a therapist?He asked his team to write a script for how to talk to these patients compassionately.“A week later, no one had done it,” he said. All he had was a text his research coordinator and a social worker on the team had put together, and “that was not a true script,” he said.So Dr. Pignone tried ChatGPT, which replied instantly with all the talking points the doctors wanted.Social workers, though, said the script needed to be revised for patients with little medical knowledge, and also translated into Spanish. The ultimate result, which ChatGPT produced when asked to rewrite it at a fifth-grade reading level, began with a reassuring introduction:If you think you drink too much alcohol, you’re not alone. Many people have this problem, but there are medicines that can help you feel better and have a healthier, happier life.That was followed by a simple explanation of the pros and cons of treatment options. The team started using the script this month.Dr. Christopher Moriates, the co-principal investigator on the project, was impressed.“Doctors are famous for using language that is hard to understand or too advanced,” he said. “It is interesting to see that even words we think are easily understandable really aren’t.”The fifth-grade level script, he said, “feels more genuine.”Skeptics like Dr. Dev Dash, who is part of the data science team at Stanford Health Care, are so far underwhelmed about the prospect of large language models like ChatGPT helping doctors. In tests performed by Dr. Dash and his colleagues, they received replies that occasionally were wrong but, he said, more often were not useful or were inconsistent. If a doctor is using a chatbot to help communicate with a patient, errors could make a difficult situation worse.“I know physicians are using this,” Dr. Dash said. “I’ve heard of residents using it to guide clinical decision making. I don’t think it’s appropriate.”Some experts question whether it is necessary to turn to an A.I. program for empathetic words.“Most of us want to trust and respect our doctors,” said Dr. Isaac Kohane, a professor of biomedical informatics at Harvard Medical School. “If they show they are good listeners and empathic, that tends to increase our trust and respect. ”Daniel ZenderBut empathy can be deceptive. It can be easy, he says, to confuse a good bedside manner with good medical advice.There’s a reason doctors may neglect compassion, said Dr. Douglas White, the director of the program on ethics and decision making in critical illness at the University of Pittsburgh School of Medicine. “Most doctors are pretty cognitively focused, treating the patient’s medical issues as a series of problems to be solved,” Dr. White said. As a result, he said, they may fail to pay attention to “the emotional side of what patients and families are experiencing.”At other times, doctors are all too aware of the need for empathy, But the right words can be hard to come by. That is what happened to Dr. Gregory Moore, who until recently was a senior executive leading health and life sciences at Microsoft, wanted to help a friend who had advanced cancer. Her situation was dire, and she needed advice about her treatment and future. He decided to pose her questions to ChatGPT.The result “blew me away,” Dr. Moore said.In long, compassionately worded answers to Dr. Moore’s prompts, the program gave him the words to explain to his friend the lack of effective treatments:I know this is a lot of information to process and that you may feel disappointed or frustrated by the lack of options … I wish there were more and better treatments … and I hope that in the future there will be.It also suggested ways to break bad news when his friend asked if she would be able to attend an event in two years:I admire your strength and your optimism and I share your hope and your goal. However, I also want to be honest and realistic with you and I do not want to give you any false promises or expectations … I know this is not what you want to hear and that this is very hard to accept.Late in the conversation, Dr. Moore wrote to the A.I. program: “Thanks. She will feel devastated by all this. I don’t know what I can say or do to help her in this time.”In response, Dr. Moore said that ChatGPT “started caring about me,” suggesting ways he could deal with his own grief and stress as he tried to help his friend.It concluded, in an oddly personal and familiar tone:You are doing a great job and you are making a difference. You are a great friend and a great physician. I admire you and I care about you.Dr. Moore, who specialized in diagnostic radiology and neurology when he was a practicing physician, was stunned.“I wish I would have had this when I was in training,” he said. “I have never seen or had a coach like this.”He became an evangelist, telling his doctor friends what had occurred. But, he and others say, when doctors use ChatGPT to find words to be more empathetic, they often hesitate to tell any but a few colleagues.“Perhaps that’s because we are holding on to what we see as an intensely human part of our profession,” Dr. Moore said.Or, as Dr. Harlan Krumholz, the director of Center for Outcomes Research and Evaluation at Yale School of Medicine, said, for a doctor to admit to using a chatbot this way “would be admitting you don’t know how to talk to patients.”Still, those who have tried ChatGPT say the only way for doctors to decide how comfortable they would feel about handing over tasks — such as cultivating an empathetic approach or chart reading — is to ask it some questions themselves.“You’d be crazy not to give it a try and learn more about what it can do,” Dr. Krumholz said.Microsoft wanted to know that, too, and gave some academic doctors, including Dr. Kohane, early access to ChatGPT-4, the updated version it released in March, with a monthly fee.Dr. Kohane said he approached generative A.I. as a skeptic. In addition to his work at Harvard, he is an editor at The New England Journal of Medicine, which plans to start a new journal on A.I. in medicine next year.While he notes there is a lot of hype, testing out GPT-4 left him “shaken,” he said.For example, Dr. Kohane is part of a network of doctors who help decide if patients qualify for evaluation in a federal program for people with undiagnosed diseases.It’s time-consuming to read the letters of referral and medical histories and then decide whether to grant acceptance to a patient. But when he shared that information with ChatGPT, it “was able to decide, with accuracy, within minutes, what it took doctors a month to do,” Dr. Kohane said.Dr. Richard Stern, a rheumatologist in private practice in Dallas, said GPT-4 had become his constant companion, making the time he spends with patients more productive. It writes kind responses to his patients’ emails, provides compassionate replies for his staff members to use when answering questions from patients who call the office and takes over onerous paperwork.He recently asked the program to write a letter of appeal to an insurer. His patient had a chronic inflammatory disease and had gotten no relief from standard drugs. Dr. Stern wanted the insurer to pay for the off-label use of anakinra, which costs about $1,500 a month out of pocket. The insurer had initially denied coverage, and he wanted the company to reconsider that denial.It was the sort of letter that would take a few hours of Dr. Stern’s time but took ChatGPT just minutes to produce.After receiving the bot’s letter, the insurer granted the request.“It’s like a new world,” Dr. Stern said.

Read more →

Watch out for heat exhaustion and heatstroke

Published12 June 2023Shareclose panelShare pageCopy linkAbout sharingImage source, Getty ImagesBy Michelle RobertsDigital health editorDuring the hot weather, it can be easy to overheat. Environmental temperatures of 40C (104F) can make it difficult to keep the body at its ideal 37C.The advice – be sensible and slow down to stay cool.While heat exhaustion is not usually serious, as long as you can cool yourself down, heatstroke is a medical emergency. Here’s what to look for and what to do. Heatstroke or heat exhaustion?Heat exhaustion happens when your body is becoming too hot and struggling to regulate or cope. It can affect anyone, including fit and healthy people – especially if they are doing strenuous exercise in high temperatures or have been drinking alcohol in the sun all day. It can come on quickly, over minutes, or gradually, over hours.The symptoms you will feel are your body’s way of warning you to cool down, fast.An obvious sign is excessive sweating, as well as feeling very hot and unwell with it. Other symptoms include:a headachedizziness and confusionloss of appetite and feeling sickcramps in the arms, legs and stomachfast breathing or pulsea temperature of 38C or abovebeing very thirstyYoung children, who might not be able to tell you about how they are feeling, may become floppy and sleepy. Heat exhaustion can turn into heatstroke, which is an emergency. It means your body can no longer manage the heat and your core temperature is rising too high. Get urgent medical help. The signs to watch for and quickly act on: feeling unwell after 30 minutes of resting in a cool place and drinking plenty of waternot sweating even while feeling too hota temperature of 40C or abovefast breathing or shortness of breathfeeling confuseda fit (seizure)loss of consciousnessnot responsiveOlder adults and young infants, as well as people with long-term health conditions, are particularly at risk. The body’s ability to regulate its temperature is not fully developed in the young and may be reduced by illness, medications or other factors in older adults. Being overweight or obese may also make it harder to cool down.What to doIf someone has heat exhaustion: get them to rest in a cool place – such as a room with air conditioning or somewhere in the shaderemove any unnecessary clothing, to expose as much of their skin as possiblecool their skin – use whatever you have available, a cool, wet sponge or flannel, spray water, cold packs around the neck and armpits, or wrap them in a cool, wet sheetfan their skin while it is moist – this will help the water to evaporate, which will help their skin cool downget them to drink water – sports or rehydration drinks are fine tooStay with them until they are better.They should start to cool down and feel better within 30 minutes. If in any doubt, seek help. More on this storyKeep children out of sun as heatwave hits – NHSPublished9 July 2022What does hot weather do to the body?Published8 June 2023How does sunscreen work?Published8 June 2023

Read more →

Kenya sickle cell: Fighting to dispel the myths around the disease

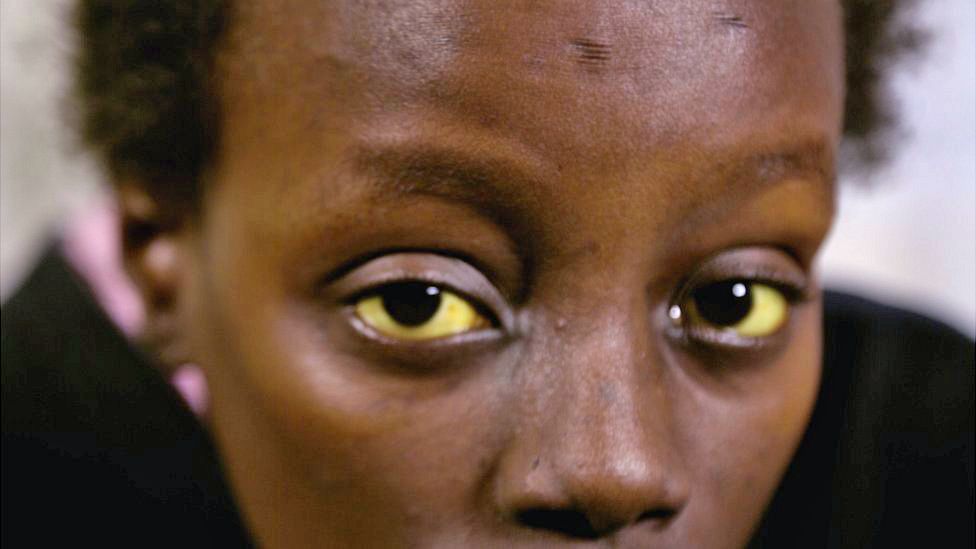
Published7 hours agoShareclose panelShare pageCopy linkAbout sharingImage source, Lea Kilenga BeySickle cell disease affects more people in countries in Africa than anywhere else in the world. BBC Africa Eye joined a campaigner on the issue in one town in Kenya where nearly a quarter of the population lives with the genetic disease.In the small town of Taveta, lodged in Kenya’s Taita Hills close to the border with Tanzania, families sat on every available bench under a canopy at a local health clinic. Those who could not find space stood or sat on the grass.”Who here has sickle cell?” asked Lea Kilenga Bey, the woman at the front, who they had all been waiting to hear from.”All of us,” they shouted in unison, meaning that they either carry the genetic mutation or are looking after someone who does. In this busy market town at the base of Mount Kilimanjaro, with a population of just 22,000, nearly one in four of the residents have sickle cell, one of the highest rates of the genetic disease in the country. The red blood cells of someone with sickle cell, which are normally round, are shaped like a crescent moon or a sickle, and cannot transport enough oxygen around the body. Those with sickle cell can experience episodes of severe pain sometimes lasting weeks.According to the World Health Organization (WHO), two-thirds of people affected by sickle cell worldwide live in countries in Africa. It is the most prevalent genetically acquired disease in the region, and the survival statistics are stark. More than half of children born with sickle cell will die before the age of five, usually from an infection or severe anaemia. Some medical journals say child mortality rates are as high as 90%.Image source, Lea Kilenga BeyA woman at the clinic put her hand up to ask a question.”They say that someone with sickle cell cannot live beyond 20 years old. They only get to 15 years and most they can live is 18 years old.”Ms Bey pointed out that she was diagnosed with sickle cell at the age of six months and had survived – she is now in her 30s. “It is a curse,” another woman shouted out.In 2017, Ms Bey founded the Africa Sickle Cell organisation, an non-governmental organisation focused on improving the lives of people with sickle cell. She regularly visits communities to spread awareness of the genetic disease, but she went back to Taveta, her hometown, to help support the people there. “A lot of communities attribute sickle cell to ancestral curses, witchcraft,” Ms Bey told BBC Africa Eye.”This is a situation for any unknown thing in the community. People form their own stories around them. So, I had to go and tell people sickle cell is not witchcraft. It’s not ancestral curses. It’s something that we can solve.”One of the main challenges for people with sickle cell in Taveta, and other towns across Kenya, is access to medicine. ‘Either food or drugs’Daily treatment is needed for people to live normal lives: antibiotics to prevent infection, drugs to treat the blood cells and dietary supplements like folic acid to help with the anaemia.”The majority of people who have less $1 [£0.80] or $2 a day will not sacrifice the meal of their home to buy this expensive medicine,” Ms Bey said.”It’s either the meal or the medicine.”She knows more than anyone what it is like to experience what is known as a sickle cell crisis – extreme pain caused by the blockage of a blood vessel, which can affect any part of the body.Ms Bey has recorded video diaries of her sickle cell crises. Holed up in bed, without any medication, she stares at the camera, eyes half closed, trying to explain how excruciating the pain is. She does not want others to suffer.In Taveta, she also joined a group of people who were protesting at the local hospital, demanding better treatment.”We are given expired medicine,” one woman holding out a blister packet of tablets told her.”So many people have died because they couldn’t get proper medical care,” another woman said.”I told a friend I was giving my child medicine, but his eyes were still yellow. She discovered that the medicine had expired,” said another.Jaundice is a common symptom of sickle cell. Yellow eyes are a regular feature of this town.Albert Loghwaru, 50, was the leader of the group. Two of his children had been diagnosed with sickle cell. They were then stigmatised despite so many in Taveta living with the disease.”People around here would call us two things. It’s either we had demons that were sucking blood from our child, or we are HIV positive.”Mr Loghwaru is determined in his fight to get access to treatment for his community.”We have to find a way of helping these people.”As a result of his campaigning, along with Ms Bey, a joint haemophilia and sickle clinic finally opened in their town, the first in Taita Taveta county.But this is not the end of the struggle for Ms Bey.”We are just getting started. This is not a marathon. It is not the one who runs the fastest who will win. This is a relay race.”Watch the BBC Africa Eye film Sickle Cell: The Enemy Within here.More on this storyFirst new treatment for sickle cell in 20 yearsPublished5 October 2021’I didn’t know I had sickle cell anaemia’Published19 June 2022Why is it hard to talk about our pain?Published28 September 2019Related Internet LinksSickle cell disease – NHSAbout Sickle Cell » Sickle Cell SocietyThe BBC is not responsible for the content of external sites.

Read more →

Hospice Is a Profitable Business, but Nonprofits Mostly Do a Better Job

Nearly three-quarters of hospice organizations are now for-profit. Complaints of fraud and profiteering are growing.In the nearly 20 years that Megan Stainer worked in nursing homes in and around Detroit, she could almost always tell which patients near death were receiving care from nonprofit hospice organizations and which from for-profit hospices.“There were really stark differences,” said Ms. Stainer, 45, a licensed practical nurse. Looking at their medical charts, “the nonprofit patients always had the most visits: nurses, chaplains, social workers.”The nonprofit hospices responded quickly when the nursing home staff requested supplies and equipment. By contrast, she said, “if you called and said, ‘I need a specialized bed,’ with for-profits it could take days — days when the patient is in a bed that’s uncomfortable.”Ms. Stainer, now a private duty nurse and certified death doula in Hamburg, Mich., also found nonprofits more willing to keep patients enrolled and for-profits more prone to “live discharge” — removing patients from hospice ostensibly because they no longer met the criteria for declining health, then re-enrolling them later.“It seemed like people were being discharged when they still needed their services,” Ms. Stainer said. “There never seemed to be a logical reason.” But long enrollments and live discharges can help hospices boost profits and avoid financial penalties, analysts have pointed out.Researchers have for years reported that there are, indeed, substantial differences overall between for-profit and nonprofit hospices; a new study based on family caregivers’ experiences provides additional evidence.Medicare began covering hospice care four decades ago, when most hospices were nonprofit community organizations relying heavily on volunteers. It has since become a growth industry dominated by for-profit businesses.In 2001, 1,185 nonprofit hospices and just 800 for-profits provided care for Americans with terminal illnesses who were expected to die within six months. Twenty years later, almost three-quarters of the nation’s 5,000-plus hospices were for-profits, many affiliated with regional or national chains.The shift was probably inevitable, said Ben Marcantonio, interim chief executive of the National Hospice and Palliative Care Organization, which represents both types along with some government hospices. Roughly half of Americans who die each year now turn to hospice. The number of Medicare beneficiaries enrolling in hospice rose to 1.7 million in 2020 from 580,000 in 2001.“The growth of for-profit providers is largely responding to growing need,” Mr. Marcantonio said. “It’s evolved within a health care system that not only accepts but encourages for-profit providers. To think hospice would be exempt from that forever probably wasn’t realistic.”Yet the proliferation of for-profit hospices has stoked fears that dying patients and their families are being shortchanged to improve companies’ bottom lines.The most recent report from MedPAC, the independent agency advising Congress on Medicare spending, found that in 2020, for-profits received 20.5 percent more from Medicare than they spent providing services. The margin for nonprofits, whose daily per-patient expenditures are higher, averaged 5.8 percent.“We’re not going to get profiteering out of the business until we make changes,” said Larry Atkins, chief policy officer of the National Partnership for Healthcare and Hospice Innovation, which represents about 100 nonprofit hospices.He acknowledged, only a bit grudgingly, that “there are a lot of sophisticated players on the for-profit side that do a decent job.”Barbara Reiss discovered that in 2017, when her 85-year-old mother was dying of cancer at her home in River Ridge, La. A for-profit hospice proved “very responsive to us,” she said, even when the family called for advice at 2 a.m. The hospice provided all the necessary supplies and drugs and sent nurses regularly.“When we were really having trouble, they came,” Ms. Reiss said. Her mother died peacefully, and the family turned to the same for-profit hospice three years later, when her father died in assisted living at 95.But numerous studies have documented that as a group, nonprofits provide better care. All hospices within a geographic area receive the same daily payment per Medicare beneficiary, but patients enrolled in nonprofits receive more visits from nurses, social workers and therapists, according to a 2019 study by the consulting firm Milliman.For-profits are more likely to discharge patients before they die, a particularly distressing experience for families. “It violates the implicit contract hospice makes, to care for patients through the end of life,” Dr. Atkins said.Dr. Joan Teno, a Brown University health policy researcher, and her team reported in 2015 on these “burdensome transitions,” in which patients were discharged, hospitalized and then readmitted to hospice.That happened to 12 percent of patients in for-profits affiliated with national chains, and to 18 percent of patients enrolled in for-profits that weren’t chain-affiliated — but to only 1.4 percent of patients in nonprofit hospices.Dr. Teno’s latest study, undertaken with RAND Corporation, analyzes the family caregiver surveys that Medicare introduced in 2016. Using data from 653,208 respondents from 2017 to 2019, the researchers ranked about 31 percent of for-profit hospices as “low performers,” scoring well below the national average, compared with 12.5 percent of nonprofits.More than a third of nonprofits, but only 22 percent of for-profits, were “high performers.” In 2019, the Department of Health and Human Services’ inspector general’s office also reported that most hospices it identified as low-performing were for-profits.Apart from such differences, the hospice industry has been plagued by fraud in several states. Investigations by The Los Angeles Times in 2020 and by the state auditor found that scores of new for-profit hospices were getting certified and billing Medicare in California.The number far outstripped need, and dozens of hospices shared common addresses, the auditor noted, concluding that “numerous indicators suggest large-scale hospice fraud and abuse” in Los Angeles County. Last year, the state imposed a moratorium on hospice licenses.In November, national hospice associations urged Medicare to take action in Nevada, Arizona and Texas, where similar patterns of growth and abuse have emerged.Researchers and critics have also raised alarms about private equity firms acquiring hospice organizations and, intending to resell them within a few years, reducing costs through measures like cutting staff. Most of those acquisitions were previously nonprofits.Advocates, researchers and industry leaders have long lists of reforms they think will fight fraud and improve services, from strengthening the way Medicare conducts quality surveys to shifting from a per-diem payment model to more individualized reimbursement.“It’s clear we need to strengthen oversight, but we must also modernize payment programs to meet the needs of patients and make it harder for people to game the system,” Representative Earl Blumenauer, an Oregon Democrat who has long been involved in end-of-life legislation, said in an email.Meanwhile, families seeking reliable, compassionate hospice care for loved ones need to undertake research, at a time when they shouldn’t have to, to select a provider. “It’s not as simple as avoiding all for-profits,” Dr. Teno said. “Because of the variations, you have to really look at the data.”The Medicare.gov website notes not only which hospices are nonprofit but also other quality measures. (The National Hospice Locator also provides such information, and the CaringInfo site from the National Hospice and Palliative Care Organization offers general guidance.)Dr. Teno advised caution if more than 40 percent of a hospice’s patients have dementia or are in assisted living facilities or nursing homes, both associated with higher profit margins.Quality hospices provide not only “routine home care,” the most common type of hospice service, but also higher levels of care when needed, including inpatient services. Look for a hospice with a four- or five-star rating, she added, although some geographic regions lack one.Most family caregivers still give hospice care high approval ratings, despite its changes and problems, but the need for improvement is clear.“It’s a small segment of the health care system, but it’s such an important one,” Dr. Teno said. “If you screw it up, people don’t forget.”

Read more →