Scientists shed light on how stressed cells sequester protein-forming mRNAs

Researchers at Weill Cornell Medicine have illuminated one of the important ways that cells respond to stress. The findings could also be relevant to Alzheimer’s, ALS and other diseases in which this mechanism may be abnormally active.
When stressed by heat, toxins or other potentially damaging factors, cells gather many of their messenger RNAs (mRNAs), molecules that carry the instructions for making proteins, into droplet-like compartments called stress granules. These granules sequester affected mRNAs, preventing them from being translated into proteins. The resulting slowdown in protein production helps the cell conserve energy, declutter and focus on repairs.
In the study, which appeared Sept. 14 in Nature Structural and Molecular Biology, the researchers confirmed that a tiny chemical modification on mRNAs, known as m6A, is key to the formation of stress granules.
“We were able to show that m6A has a primary role in driving mRNAs into these granules during cell stress,” said study senior author Dr. Samie Jaffrey, the Greenberg-Starr Professor of Pharmacology at Weill Cornell Medicine.
The study’s first author, Dr. Ryan Ries, was a Weill Cornell Graduate School of Medical Sciences doctoral student during the research.
Understanding How Stress Granules Form
Stress granules contain many different mRNAs from the cell, but not a random selection. Dr. Jaffrey and his team previously showed that mRNAs that are found in stress granules are often chemically tagged with a small cluster of atoms called a methyl group which attaches to adenosine, one of the mRNA building blocks. The resulting mRNA has regions that are enriched in N6-methyladenosine, or m6A. They also found that m6A-rich regions bind to YTHDF proteins — the more m6A an mRNA has, the more YTHDF proteins are present. The large amount of YTHDF proteins is needed to allow the m6A-mRNA-YTHDF complexes to accumulate into stress granules.

Read more →

Drug trial shows reduced abnormal bone formation in those with fibrodysplasia ossificans progressiva

A multisite, international phase 2 trial evaluating the investigational drug garetosmab has shown that it reduced soft-tissue flare-ups significantly and prevented new areas of abnormal bone formation in patients with fibrodysplasia ossificans progressiva (FOP).
Kathryn Dahir, MD, professor of Medicine in the Division of Endocrinology and Diabetes, served as the principal investigator at Vanderbilt University Medical Center for the randomized, double-blinded, placebo-controlled trial to study the efficacy and safety of garetosmab, a human monoclonal antibody. Garetosmab binds to activin A, a protein in the body related to growth, and blocks its ability to activate FOP-mutant ACVR1.
The findings, published this week in the journal Nature Medicine, give hope to individuals with the rare disease that effects 1 out of 1 million individuals in the United States. FOP is caused by mutations in the gene ACVR1 which lead to abnormal formation of bone outside of the normal skeleton in soft tissue including muscles, tendons and ligaments throughout the body.
“Garetosmab decreased total lesion activity by nearly 25%, including new and existing lesions, as compared to placebo, and showed a remarkable 90% decrease in the number of new bone lesions. The prevention of new, heterotopic bone is of critical importance to the treatment of FOP,” said Dahir. “Patient-reported soft tissue flare-ups — with symptoms such as fever, pain, swelling and stiffness — were also reduced by half. As flare-ups often precede the formation of new lesions, we are encouraged that this investigational drug may help prevent the progression of FOP.
“The loss of mobility created by the abnormal bone growth is cumulative and steadily limits the ability of persons with FOP to perform even the most basic activities. It’s time for these patients and their families to feel hope with the possibility of a treatment that can make a real difference in their lives. I’m grateful to the patients and their families who participated in the trial, and we look forward to continuing to gather evidence on the safety and efficacy of this treatment.”
In the trial, 44 adults enrolled in the multicenter study who were diagnosed with FOP received garetosmab or a placebo every four weeks and were evaluated for new bone lesions by the using whole body positron emission tomography (PET) with sodium fluoride and low-dose computed tomography (CT) scans at baseline, eight weeks, 28 weeks and 56 weeks. At 28 weeks, all subjects began an open-label period in which both patients and researchers knew which treatment was being administered. Patients in the placebo group could choose to begin receiving garetosmab.
Brentwood, Tennessee, resident Sharon Kantanie, who was diagnosed with FOP at age 6, was one of the participants in the drug trial at VUMC. When the study shifted to the open-label period she learned she had received garetosmab from the beginning. Kantanie primarily experienced minor dermatological side effects. She is happy the results have been published and that further investigation of the drug’s efficacy and safety is now in progress.

Read more →

Brazil's diversity makes country a testing ground for a global stem cell biobank, scientists say

A biobank for all, in which a person from any background could find a bone marrow donor for a stem cell transplant, is a major goal for stem cell science. While repositories of cell lines that could be a match for most patients are successfully materializing in some countries with genetically homogenous populations like Japan and the United Kingdom, how many more we need for a universal solution remains unknown. In a study appearing September 28 in the journal Stem Cell Reports, researchers estimate at least 559 distinct cell lines would be required to cover 95% of the more diverse, and globally representative, people of Brazil.
“Considering the possibility of creating a global network of induced pluripotent stem (iPS) cell banks, we hypothesize that, given the admixture of African, Indigenous, and European ancestries in Brazil, our genetic diversity might provide iPS cells that may cover other countries,” write the research team, led by Antonio Carlos Campos de Carvalho of the Federal University of Rio de Janeiro and Marcio Lassance Martins de Oliveira of Brazil’s National Institute of Cardiology, Ministry of Health.
Donor compatibility reduces the chances that a patient will reject a stem cell transplant. In cases where a transplant is required, such as with severe blood diseases, family members are often the first to offer to donate their bone marrow, but only 12% of relatives end up being a match. A global biobank could reduce these pressures, but it is unknown how many samples would provide an adequate diversity of cell lines.
To find the ideal number of donor cell lines in Brazil, the research team used data from the Brazilian National Registry of Bone Marrow Donors (REDOME). From over 4 million individuals, the researchers identified nearly 2,000 cell lines that could act as potential universal donors. The team then calculated how many of these cell lines would be a match for most of the Brazilian population, and they estimated 51, 157, 267, and 559 cell lines would provide 50%, 75%, 85%, and 95% coverage, respectively. They also predicted over 4 million individuals would need to be tested to cover 99% of Brazilians.
Notably, only 30 cell lines were enough to be a donor match for almost 40% of Brazilians. Using the Allele Frequency Net Database (AFND, which compiles genetic data from 369 studies and over 10 million individuals worldwide), the investigators found these same 30 cell lines could cover about 40% of Caucasians, 12% of African descendants, 25% of Alaska Natives and Native Americans, and less than 4% of the Asian population in the USA.
“This discrepancy between different populations shows the importance of an initiative to constitute a World iPS Bank, to which Brazil could contribute considerably,” the researchers write. “We hope that the publication of the current data will entice the existing bone marrow donor registries to share data that would allow more precise calculations of the dimension of a global iPS cell bank to supply the world population with this important source of advanced therapy for regenerative medicine.”

Read more →

New study provides evidence for more effective brain-based treatment of chronic back pain

A new study in JAMA Network Open may provide key answers to how to help people experiencing chronic back pain.
The study, published today, examined the critical connection between the brain and pain for treating chronic pain. Specifically, they looked at the importance of pain attributions, which are people’s beliefs about the underlying causes of their pain, to reduce chronic back pain severity.
“Millions of people are experiencing chronic pain and many haven’t found ways to help with the pain, making it clear that something is missing in the way we’re diagnosing and treating people,” said the study’s first author Yoni Ashar, PhD, assistant professor of internal medicine at the University of Colorado Anschutz Medical Campus.
Ashar and his team tested whether the reattribution of pain to mind or brain processes was associated with pain relief in pain reprocessing therapy (PRT), which teaches people to perceive pain signals sent to the brain as less threatening. Their goal was to better understand how people recovered from chronic back pain. The study revealed after PRT, patients reported reduced back pain intensity.
“Our study shows that discussing pain attributions with patients and helping them understand that pain is often ‘in the brain’ can help reduce it,” Ashar said.
To study the effects of pain attributions, they enrolled over 150 adults experiencing moderately severe chronic back pain in a randomized trial to receive PRT. They found two-thirds of people treated with PRT reported being pain-free or nearly so after treatment, compared to only 20% of placebo controls.
“This study is critically important because patients’ pain attributions are often inaccurate. We found that very few people believed their brains had anything to do with their pain. This can be unhelpful and hurtful when it comes to planning for recovery since pain attributions guide major treatment decisions, such as whether to get surgery or psychological treatment,” said Ashar.

Read more →

Decoding the complexity of Alzheimer's disease

Alzheimer’s disease affects more than 6 million people in the United States, and there are very few FDA-approved treatments that can slow the progression of the disease.
In hopes of discovering new targets for potential Alzheimer’s treatments, MIT researchers have performed the broadest analysis yet of the genomic, epigenomic, and transcriptomic changes that occur in every cell type in the brains of Alzheimer’s patients.
Using more than 2 million cells from more than 400 postmortem brain samples, the researchers analyzed how gene expression is disrupted as Alzheimer’s progresses. They also tracked changes in cells’ epigenomic modifications, which help to determine which genes are turned on or off in a particular cell. Together, these approaches offer the most detailed picture yet of the genetic and molecular underpinnings of Alzheimer’s.
The researchers report their findings in a set of four papers appearing today in Cell. The studies were led by Li-Huei Tsai, director of MIT’s Picower Institute for Learning and Memory, and Manolis Kellis, a professor of computer science in MIT’s Computer Science and Artificial Intelligence Laboratory (CSAIL) and a member of the Broad Institute of MIT and Harvard.
“What we set out to do was blend together our computational and our biological expertise and take an unbiased look at Alzheimer’s at an unprecedented scale across hundreds of individuals — something that has just never been undertaken before,” Kellis says.
The findings suggest that an interplay of genetic and epigenetic changes feed on each other to drive the pathological manifestations of the disease.
“It’s a multifactorial process,” Tsai says. “These papers together use different approaches that point to a converging picture of Alzheimer’s disease where the affected neurons have defects in their 3D genome, and that is causal to a lot of the disease phenotypes we see.”
A complex interplay

Read more →

Grandparent childcare may not help the wellbeing of mums or reduce mother-child conflict, study suggests

Grandparent childcare for toddlers doesn’t have an impact on the wellbeing of their mothers, a new study suggests.
Extra help from another generation alone doesn’t help mother- child closeness or reduce mother-child conflict, researchers have found.
Researchers who examined information from a sample of mothers could find no statistical link between their children spending time with grandparents at age three and better social and emotional development when they were seven, or better maternal wellbeing and mother-child relationship at age three.
The academics have called for more investment in child and maternal mental health and wellbeing in early childhood. Parents who took part in the study indicated grandparents were their primary source of childcare, and they had less other support.
The study was carried out by Nevra Atış Akyol, from Sivas Cumhuriyet University, Turkey, Derya Atalan Ergin, from Cappadocia University, Turkey, and Angeliki Kallitsoglou, from the University of Exeter.
The researchers examined information from 1,495 mothers and their children. The findings showed that time spent in the care of grandparents for at least six months was not significantly associated with better maternal mental health and wellbeing and mother-child relationship, or better social and emotional outcomes for children when they were seven.
The study, which used data from the Millennium Cohort Study, shows poor maternal wellbeing at age three predicted poor child social and emotional outcomes at age seven.

Read more →

As Covid Infections Rise, Nursing Homes Are Still Waiting for Vaccines

Now that the U.S. government has stepped back from issuing vaccines, long-term care operators have yet to start administering shots to protect one of the most vulnerable populations.“Covid is not pretty in a nursing home,” said Deb Wityk, a 70-year-old retired massage therapist who lives in one called Spurgeon Manor, in rural Iowa. She has contracted the disease twice, and is eager to get the newly approved vaccine because she has chronic leukemia, which weakens her immune system.The Centers for Disease Control and Prevention approved the latest vaccine two weeks ago, and the new shots became available to the general public within the last week or so. But many nursing homes will not begin inoculations until well into October or even November, though infections among this vulnerable population are rising, to nearly 1 percent, or 9.7 per 1,000 residents, as of mid-September, from a low of 2.2 per 1,000 residents in mid-June.“The distribution of the new Covid-19 vaccine is not going well,” said Chad Worz, the chief executive of the American Society of Consultant Pharmacists. “Older adults in those settings are certainly the most vulnerable and should have been prioritized.”With the end of the formal public health emergency in May, the federal government stopped purchasing and distributing Covid vaccines. That has added new complications for operators of nursing homes, who have encountered resistance throughout the pandemic in persuading people, especially employees, to receive yet another round of shots.The coronavirus decimated nursing homes during the first two years of the pandemic, killing more than 200,000 residents and staff members. Elizabeth Sobczyk, the project director of Moving Needles, a C.D.C.-funded initiative to improve adult immunization rates in long-term care facilities, said that without a government agreement to purchase the shots, vaccine manufacturers would only make large quantities once C.D.C. experts recommended approval.“Then they need to be F.D.A. inspected — we want safe vaccines — then there is contracting and roll out,” Ms. Sobczyk said. “So I completely understand the frustration, but also why the availability wasn’t immediate.”Even once the shots are available, nursing homes face continuing resistance to the vaccines among nurses and aides. Without state mandates for workers to be vaccinated, most nursing homes are relying on persuasion, and that is often proving difficult.“People want Covid-19 to be in the rearview mirror,” said Leslie Eber, medical director of Orchard Park Health Care Center in Centennial, Colo. “We’re going to have to remind people more this year that Covid-19 is not benign. Maybe it’s a cold for some people, but it’s not going to be a cold for the folks I care for.”Only 62 percent of nursing home residents are up-to-date on their vaccines, meaning they have received the last booster available before this month’s new shot, according to federal data from mid-September. That’s an improvement over the 38 percent rate at the start of October 2022.But only 25 percent of nursing home employees are up-to-date, which is close to last October’s rate.In a written statement, the Department of Health and Human Services said that it would be identifying long-term care facilities with low vaccination rates and reaching out to ensure “proven infection prevention and control measures are being implemented to protect seniors.”This year, in addition to the Covid and flu shots, nursing homes will offer a new vaccine for R.S.V., meaning many residents will receive three shots.Alisha Jucevic for The New York TimesThis year, more nurses and aides will have to obtain shots at drugstores or health centers on their personal time, rather than at work. Many homes are running clinics, with their long-term care pharmacies supplying the vaccine as they did before, but they face extra bureaucratic hassles in billing insurers for the vaccine for both residents and employees.On top of that, homes are rolling out a new vaccine for a dangerous respiratory virus, R.S.V., which will be a third shot for many residents, along with vaccines for Covid and the flu.The trio of vaccines will create more administrative complexity for nursing homes because now they must bill Medicare to be reimbursed for the shots. The Covid vaccine is charged to Medicare Part B, which covers outpatient and physicians’ services, but the R.S.V. vaccine must be billed to Medicare Part D, the prescription drug benefit.“The United States has been phenomenal in screwing up vaccinations,” said David Nace, chief medical officer of UPMC Senior Communities in Pittsburgh. “This idea that some are under Part B and some are under Part D and some can be billed by a pharmacy — who in God’s name came up with this?”While Medicare will pay for vaccines for most nursing home residents, employees may face private insurance red tape and, for a small group, potential out-of-pocket costs.Leslie Frane, an executive vice president of Service Employees International Union, which represents more than 134,000 workers in 1,465 nursing homes, said that many homes had stopped running clinics in their facilities and had told workers to go to the drugstore to get vaccinated. She said this would lead to more workers skipping their shots.“There’s very little time, given how many nursing home workers work multiple jobs,” she said.The C.D.C. has arranged for 25 to 30 million people who lack health insurance or whose insurance doesn’t cover the complete cost of the vaccine to get free Covid shots at select pharmacies, health centers and medical offices listed on www.vaccines.gov. Ms. Frane said the program was not well-known among workers, and Mr. Worz said distribution was favoring the large pharmacy chains, slowing access in rural communities. Of the nation’s 19,400 independent pharmacies, federal officials said 627, many in rural areas, were enrolled in the program and 100 more were being added.A big obstacle, though, continues to be resistance to vaccination among nurses and aides. Like many facility owners, Avalon Health Care Group, which owns or operates more than a dozen nursing homes in western states, is not mandating staff be vaccinated. Dr. Sabine von Preyss-Friedman, Avalon’s chief medical officer, says she tries to address the reasons with each worker and won’t abandon the push.“We’re not going to just say, ‘OK, everyone get vaccinated,’ and then forget about it,” she said.Avalon’s homes have used modest financial incentives to encourage staff members to get vaccinated. Some have organized contests between different units, with the winner getting prizes like a pizza party or a drawing for a gift certificate from a department store, and those efforts will resume this year.Jim Wright, the medical director of Our Lady of Hope Health Center and two other nursing homes in Richmond, Va., said that rewards and respectful persuasion were not enough to sway his homes’ employees. They tend to be in their 20s and 30s, he said, and are not worried about catching Covid, which many have already weathered.“They most likely will not do it to protect the residents or protect themselves,” he said. “I don’t know what the answer is.”Sheena Bumpas, a nursing assistant in Duncan, Okla., and vice chair of the National Association of Health Care Assistants, planned to get this season’s shot, but said some of her colleagues would not.“Now that the public health emergency has ended, I think people are done with it,” she said.The trio of vaccines will create more administrative complexity for nursing homes since this year they must bill Medicare to be reimbursed for the shots.Alisha Jucevic for The New York TimesEdenwald Senior Living, a nursing home within a retirement community in Towson, Md., is requiring its workers be vaccinated unless they can justify an exemption for medical or religious reasons.As of Sept. 10, about three-fourths of the home’s workers were up-to-date with their previous Covid vaccines, triple the national rate for nursing home employees, according to federal records.Edenwald is relying on the Giant supermarket pharmacy to administer the shots in the auditorium of its independent living section. Sign-up sheets have already been distributed for clinics later this month. The home is billing workers’ insurance for the shots, but managers at the home said it would pay for employees without health coverage.“This is our seventh clinic for Covid,” said Meghan Curtis, Edenwald’s director of care management. “We’ve kind of got it down pat.”Swati Gaur, the medical director of three nursing homes affiliated with Northeast Georgia Health System, said some homes might offer recalcitrant employees the Novavax vaccine. It relies on more traditional virus-blocking technology than the Moderna or Pfizer shots, which use messenger RNA.“We are basically saying, ‘Why are you not taking the vaccine? Have you thought about Novavax? It’s manufactured like the flu vaccine,’” Dr. Gaur said.For the first time, nursing home residents will be offered a vaccine for respiratory syncytial virus, or R.S.V. The virus causes the hospitalizations of as many as 160,000 people over age 65 each year, killing up to 10,000. Most nursing homes are coupling the flu vaccine with either the Covid vaccine or the R.S.V. vaccine, but are not attempting to give all three simultaneously.Dr. Gaur said that the novelty of the vaccine and people’s relative unfamiliarity with R.S.V. meant that clinicians would need to spend more time explaining the reason for the shots.Spurgeon Manor, the nursing home where Ms. Wityk lives, is partnering with the pharmacy at a nearby Hy-Vee grocery store to provide the Covid shot, most likely in early October, to 85 residents of the home and an adjoining assisted living center as well as employees.Alana Marean, its assistant director of nursing, said that workers would be encouraged to receive the shots, but she guessed that not even half would do so. “There’s a lot of stigma out there about it,” she said.Lee Giese, 95, a retired truck driver who lives at the home, said he was looking forward to the latest shot after coming down with Covid last winter. He said he believed his earlier vaccinations helped protect him from more serious symptoms.He said he expected most residents of his facility would get the shots, but a few would refuse. “Some people have a death wish,” he said.Jordan Rau and Tony Leys are reporters for KFF Health News, a nonprofit news organization. For this story, Mr. Leys reported from Dallas Center, Iowa, and Mr. Rau reported from Washington, D.C.

Read more →

Millions wrongly labelled with penicillin allergy, pharmacists warn

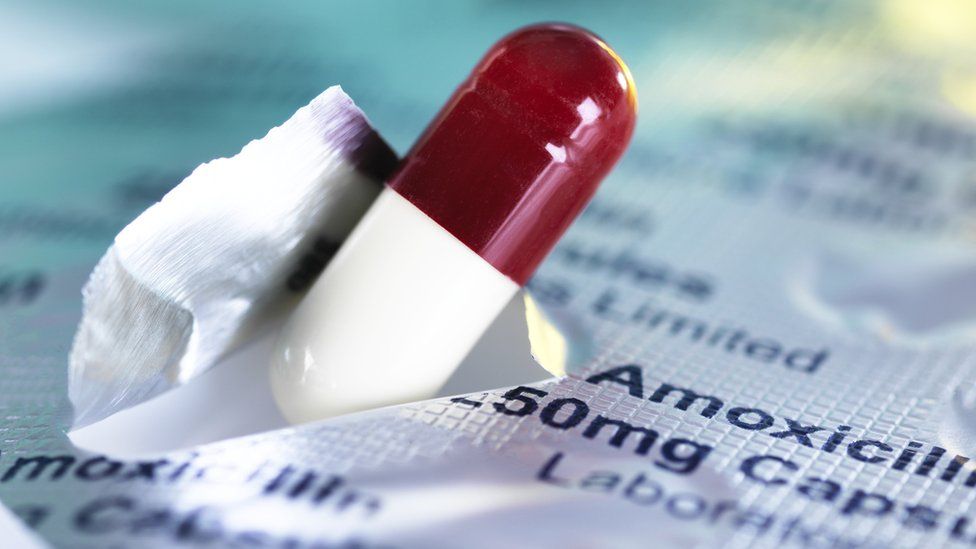
Published1 hour agoShareclose panelShare pageCopy linkAbout sharingImage source, Getty ImagesBy Philippa RoxbyHealth reporterMillions of people wrongly believe they are allergic to penicillin, which could mean they take longer to recover after an infection, pharmacists say.About four million people in the UK have the drug allergy on their medical record – but when tested, 90% of them are not allergic, research suggests.The Royal Pharmaceutical Society says many people confuse antibiotic side-effects with an allergic reaction.Common allergic symptoms include itchy skin, a raised rash and swelling.Nausea, breathlessness, coughing, diarrhoea and a runny nose are some of the others.But antibiotics, which treat bacterial infections, can themselves cause nausea or diarrhoea and the underlying infection can also lead to a rash.And this means people often mistakenly believe they are allergic to penicillin, which is in many good, common antibiotics.These are used to treat chest, skin and urinary tract infections – but if people are labelled allergic, they are given second-choice antibiotics, which can be less effective.’Low risk’Research has previously found there were six extra deaths per 1,000 patients in the year after they received a non-penicillin antibiotic to treat an infection.Tase Oputu, from the RPS, said: “Many individuals are at low or very low risk of having a genuine penicillin allergy and we often find that after careful investigation that they can take penicillin safely.” She urged anyone in that position to ask questions about their allergy label from their pharmacist next time they visited their GP.A childhood allergy or one reported many years ago can also settle down and no longer be an issue.Mild to moderate allergic reactions can usually be treated with antihistamines, but more severe reactions can be life-threatening. Signs of a reaction include:a raised, itchy skin rash (urticaria, or hives)coughingwheezing and tightness of the throat, which can cause breathing difficulties – call 999 if the person is struggling to breatheCommon side-effects of antibiotics can include: nauseabloating and indigestiondiarrhoea Anyone who has had a severe reaction in the past would need allergy testing and may be told never to take penicillin, Ms Oputu added.The charity Allergy UK said many people had a label of penicillin allergy from early childhood that could be carried with them for the rest of their life without ever being investigated.”There is now a national effort to look into this and the best way to approach it,” clinical-services head Amena Warner said.There are long waiting times to see a specialist allergist for a definitive test.But experts say there are other ways to remove a penicillin-allergy label – compiling a detailed history of symptoms is the main method. This can be given to a healthcare specialist as part of a consultation.Related Internet LinksAntibiotics – NHSAllergies – NHSRoyal Pharmaceutical Society – RPSThe BBC is not responsible for the content of external sites.

Read more →

Safer brain surgery using AI possible within two years

Published10 hours agoShareclose panelShare pageCopy linkAbout sharingBy Tulip MazumdarGlobal health correspondentBrain surgery using artificial intelligence could be possible within two years, making it safer and more effective, a leading neurosurgeon says.Trainee surgeons are working with the new AI technology, to learn more precise keyhole brain surgery. Developed at University College London, it highlights small tumours and critical structures such as blood vessels at the centre of the brain.The government says it could be “a real game-changer” for healthcare in the UK. Critical structuresBrain surgery is precise and painstaking – straying a millimetre the wrong way could kill a patient instantly. Avoiding damaging the pituitary gland, the size of a grape, at the centre of the brain, is critical. It controls all the body’s hormones – and any problems with it can cause blindness. “If you go too small with your approach, then you risk not removing enough of the tumour,” National Hospital for Neurology and Neurosurgery consultant neurosurgeon Hani Marcus says.”If you go too large, you risk damaging these really critical structures.” The AI system has analysed more than 200 videos of this type of pituitary surgery, reaching, in 10 months, a level of experience it would take a surgeon 10 years to gain.Image source, BBC “Surgeons like myself – even if you’re very experienced – can, with the help of AI, do a better job to find that boundary than without it,” Mr Marcus says.”You could, in a few years, have an AI system that has seen more operations than any human has ever or could ever see.” Trainee Dr Nicola Newell also finds it “very helpful”. “It helps me orientate myself during mock surgery and helps identify what steps and what stages are coming up next,” she says.’Marvel superhero’AI government minister Viscount Camrose says: “AI makes everybody massively more productive whatever it is you do.”It kind of almost makes you the Marvel superhero version of yourself.”He said this type of technology could be a game-changer for healthcare, improving outcomes for everyone and offering a “very promising” future.University College London (UCL) is one of 22 universities recently given government money to help revolutionise healthcare in the UK.Engineers, clinicians and scientists are working together on the project at the Wellcome / Engineering and Physical Sciences Research Council (EPSRC) Centre for Interventional and Surgical Sciences.Follow @tulipmazumdar on X, formerly known as Twitter.More on this storyWoman’s bowel cancer spotted by AIPublished21 AprilAI cuts treatment time for cancer radiotherapyPublished27 JuneRelated Internet LinksUniversity College LondonThe BBC is not responsible for the content of external sites.

Read more →

Peace Corps Sued Over Mental Health Policy

Applicants have challenged the Peace Corps practice of rescinding invitations to applicants on the basis of mental health conditions.Lea Iodice was thrilled to hear that the Peace Corps had accepted her application and was sending her to Senegal as a community health care worker. She shared the good news with her roommates, her family and her favorite professor and daydreamed about her last day at her job, managing a gym called SnapFitness.She was crushed, about a month later, to receive a letter from the Peace Corps Office of Medical Services saying that her offer was being rescinded because she was in treatment for anxiety. Though she had been in therapy to manage occasional panic attacks, she had never taken any psychiatric medication, been hospitalized or engaged in any kind of self-harm.“The reason for medical nonclearance is that you are currently diagnosed with an unspecified anxiety disorder,” read the letter, which appeared in her online application portal. “You indicated that your anxiety symptoms of increased heart rate and queasiness recur during periods of stress, which is likely to occur during service.”Searching online, Ms. Iodice discovered that her experience was not uncommon. For years, comparing notes under anonymous screen names, Peace Corps applicants have shared stories about being disqualified because of mental health history, including common disorders like depression and anxiety.The practice is the subject of a lawsuit filed this week in federal court, accusing the Peace Corps of discriminating against applicants with disabilities in violation of the Rehabilitation Act, which prohibits discrimination in programs receiving federal funds.The lawsuit, which is seeking class-action status from the U.S. District Court for the District of Columbia, includes accounts from nine people whose Peace Corps invitations were rescinded for mental health reasons. The suit alleges that those decisions were made without considering reasonable accommodations or making individualized assessments based on current medical knowledge.In a statement, a Peace Corps official said he could not comment on pending litigation, but added that “the health, safety and security of Volunteers are the Peace Corps’s top priority.”“The agency has a statutory responsibility to provide necessary and appropriate medical care for Volunteers during service,” said Jim Golden, acting associate director of the Office of Health Services, in a statement. “Many health conditions — including mental health care — that are easily managed in the U.S. may not be able to be addressed in the areas where Peace Corps Volunteers are assigned.”He said each candidate’s medical history is assessed individually to determine whether the agency can support the individual’s needs. The three plaintiffs in the lawsuit are not identified by name in the court filings. But other Peace Corps applicants described rescinded offers as a major blow at a vulnerable time in their lives, throwing post-college plans into doubt and forcing them to explain to family, friends and supporters that they had been rejected because of a mental health condition.“It was really heartbreaking to be dismissed like that,” said Ms. Iodice, now 26, who is not a party to the lawsuit. “It took a lot of processing to get over the initial feeling of unworthiness.”The Peace Corps medically screens accepted applicants before sending them overseas to ensure that they do not face health crises when they are in locations where specialized care may not be available. Similar screenings are used in the State Department and the military.But those policies are coming under pressure from legal activists. Early this year, the State Department agreed to pay $37.5 million to settle a class-action lawsuit, filed 16 years ago, challenging a hiring requirement that an applicant should be able to work in any State Department overseas post without the need for ongoing medical treatment.In recent years, the Peace Corps has deployed around 7,000 volunteers to more than 60 nations, according to recent figures from the Congressional Research Service. A review of the medical clearance system found that, in 2006, around 450 applicants were medically disqualified from serving.Carol Spahn, director of the Peace Corps.Michael Brochstein/Sipa USA, via Alamy Live News“I was shocked, at first, at how broad and antiquated some of these policies seem,” said Megan Schuller, legal director of the Bazelon Center for Mental Health Law, which, along with Bryan Schwartz Law, is representing the plaintiffs.One party to the lawsuit filed on Tuesday, Teresa, 22, who asked to be identified by her middle name out of concern that stigma would damage her employment prospects, had been accepted this past January for a volunteer position in Mexico working on climate change awareness.In March, before her planned departure, she was told that she had failed her medical clearance because of her history of treatment for anxiety and depression. She appealed the decision but was denied.Like many undergraduates, she had struggled during the isolation of the pandemic and attended therapy and took an antidepressant medication in 2020, never considering that these treatments might disqualify her from serving in the Peace Corps, she said.“There was part of me that thought, This can’t happen,” she said. “I do not know a single person throughout my whole college experience who didn’t struggle with their mental health.”The letter informing her of her nonclearance cited “active symptoms of anxiety, increased heart rate, inability to sit still, inability to say no,” all symptoms noted down by her therapist in 2021, she said. She spent the weeks around college graduation explaining, again and again, that she wouldn’t be going to Mexico after all.“It’s really humiliating to tell people that you got in and were then rejected because of your mental health,” said Teresa, who is now training to be a paralegal.Another party to the case, Anne, 34, who also asked to be identified by her middle name out of concern for stigma, was offered a Peace Corps position in Mongolia teaching at the university level.On her medical clearance forms, she shared that she had made two suicide attempts at age 15 and was hospitalized at the time, she said in an interview. Since then, however, she had lived abroad as an exchange student and worked for more than a decade as a public school English teacher with no recurrence of suicidal behavior.Her rejection letter, which arrived in November, said that she was assessed as a high risk for a recurrence of suicidal behavior. She scrambled to appeal the decision but was denied. “When you get a denial based on something from half your life ago, it feels like a punishment for being honest, and it feels like part of your past that you can’t escape,” said Anne, who teaches at a high school. “I was very upset. I was confused and trying to figure out how to do it — to save this dream.”Complaints over the policy have simmered for years in online forums and were the subject of a Change.org petition in 2019 and coverage this year in Worldview magazine, a news site for the National Peace Corps Association.Applicants are increasingly forthcoming in discussing their experiences with medical clearance, said Jade Fletcher-Getzlaff, 33, who outlined her own denial and successful appeal in a YouTube video in 2019. With each wave of deployments, she said, she receives between five and 10 inquiries from applicants who have been disqualified because of mental health conditions.“As more people are seeking therapy, and more openly talking about these issues, I think it may be coming up more often,” she said in an interview from Japan, where she now teaches, after serving as a Peace Corps volunteer in Cambodia.Rates of anxiety and depression among young U.S. adults have risen sharply in recent years. In 2020, a Centers for Disease Control and Prevention study found that 63 percent of adults aged 18 to 24 years reported mental health symptoms, compared with 31 percent of all adults. Young adults also expressed greater need for mental health treatment, with 41 percent of adults aged 19 to 25 reporting unmet needs, compared with 26 percent of all adults.Kirstine Schatz, 24, who is currently serving as a Peace Corps volunteer in Morocco, said she was initially denied a medical clearance because she took sertraline, a common antidepressant, for six months on the recommendation of her primary care physician. She discontinued the medication seven months before applying and never received any mental health diagnosis, she said, but she was informed that she was denied medical clearance because the stressful environment of the Peace Corps might trigger a relapse. Ms. Schatz appealed the decision, emphasizing that she had been off the medication and stable for six months, and the decision was overturned. She urged the agency to change its screening policy. “They are missing out on so many amazing people because of this archaic mind-set they have on mental health,” she said. “It’s 2023. They need to figure it out.”As for Ms. Iodice, she never appealed her initial rejection and is still at SnapFitness, where she is the general manager. She said she had no regrets about receiving therapy, even though it might have kept her from serving with the Peace Corps in Senegal.“If I had applied before I went to therapy, I could have gotten there, but I would have been a way worse worker, in my opinion,” she said. “In my perspective, I am a stronger person. I know myself better. I know how to cope.”

Read more →